
A vaginal hysterectomy is one of the approved surgical methods for removing the uterus without the need for an incision in the abdominal wall. This procedure is used to treat a range of common gynecological conditions, such as fibroids, heavy uterine bleeding, uterine prolapse, and certain cancerous or precancerous conditions.
This type of hysterectomy is less invasive than traditional abdominal surgery and is typically associated with a shorter hospital stay, less postoperative pain, and a faster recovery. However, the choice of this approach depends on several medical factors, most notably the size and shape of the uterus, the reason for the surgery, and the patient’s overall health.
What is a vaginal hysterectomy?
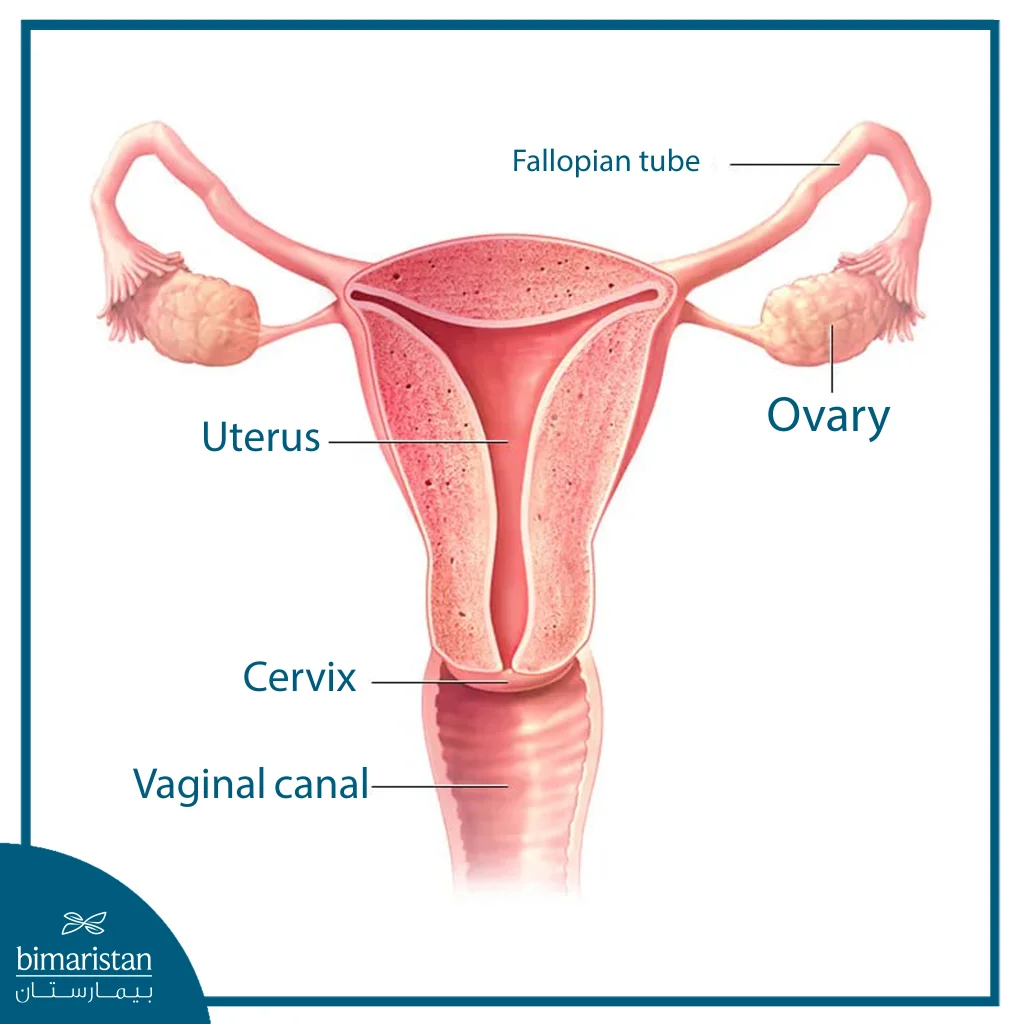
A vaginal hysterectomy is a surgical procedure in which the uterus is removed through the vagina without making an external incision in the lower abdomen. During the procedure, the surgeon detaches the uterus from its supporting tissues, including ligaments and blood vessels, and the upper part of the vagina; the ovaries and fallopian tubes may also be detached if necessary. After the uterus is completely freed, it is removed through the vaginal canal, and the vaginal opening is then surgically closed.
The procedure often involves the removal of the cervix as well; this is known as a total hysterectomy. In some cases, one or both ovaries may be removed along with the fallopian tubes; this is called a total hysterectomy with salpingo-oophorectomy. This approach is considered one of the least invasive methods of hysterectomy and is preferred whenever medical conditions permit, especially in benign cases.
Indications for Vaginal Hysterectomy
Vaginal hysterectomy is performed to treat a number of conditions affecting the female reproductive system, particularly when medication or less invasive procedures fail to control symptoms. This procedure is the preferred option for benign conditions whenever the anatomical conditions are suitable. The main indications include the following:
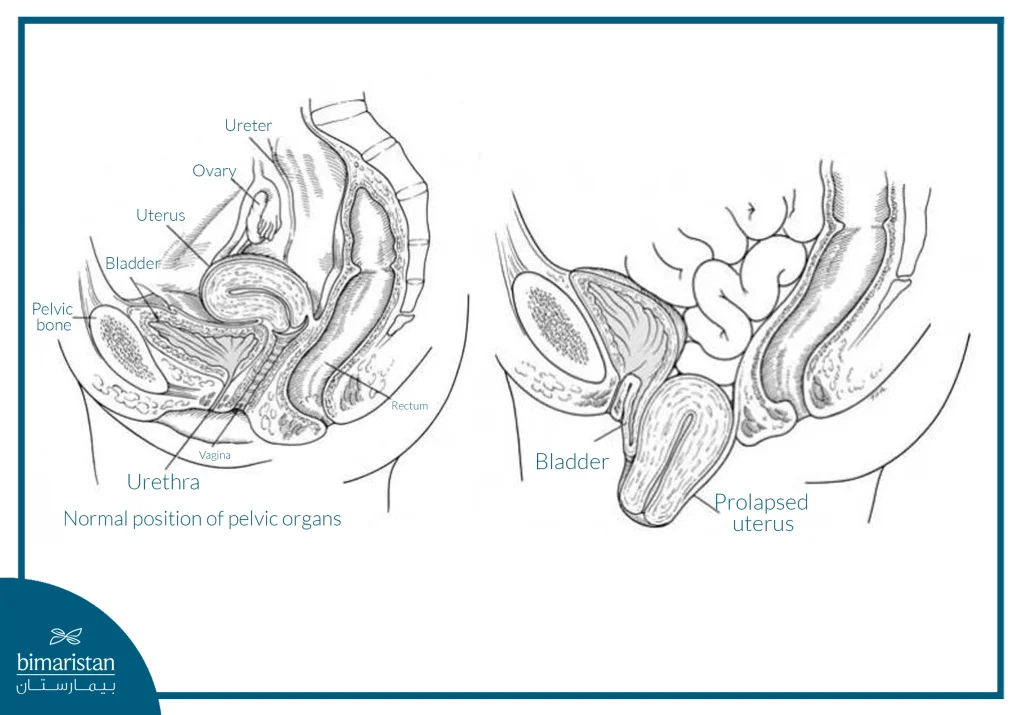
- Uterine prolapse: This is the most common cause, in which the uterus descends into the vagina due to weakness in the ligaments and supporting tissues of the pelvis, causing a feeling of pressure, urinary incontinence, or difficulty with bowel movements.
- Uterine fibroids: Especially when they cause heavy bleeding, anemia, pelvic pain, or pressure on the bladder, provided that the uterus is small enough to be removed vaginally.
- Abnormal or heavy uterine bleeding: When there is no response to medication or conservative procedures such as curettage or laparoscopic resection.
- Chronic pelvic pain associated with the uterus: After ruling out other causes and confirming that the uterus is the primary source of the pain.
- Adenomyosis: When it causes uterine enlargement and painful, heavy menstrual periods, and other treatments have not been successful.
- Endometriosis: In certain selected cases, although laparoscopy or robotic surgery is more common.
- Certain types of cancer or precancerous changes, such as endometrial or cervical cancer in its early stages, depending on the evaluation of the case.
It is important to emphasize that a hysterectomy is not always the first option; rather, it is typically considered a treatment option when other alternatives are ineffective or unsuitable.
Who is a suitable candidate for a vaginal hysterectomy?
Not all female patients are eligible for this type of surgery; the decision depends on a thorough clinical and anatomical evaluation. A patient is considered a suitable candidate in the following cases:
- The presence of obvious uterine prolapse, especially if accompanied by vaginal wall prolapse
- A uterus of average or small size that can be removed vaginally without significant technical difficulty
- The absence of severe abdominal adhesions or a complex surgical history may hinder safe access
- No need for extensive abdominal exploration or advanced oncologic surgery
- Overall stable health condition that allows for anesthesia and surgery
- No future desire to become pregnant, as pregnancy is no longer possible after a hysterectomy
The final decision is made after a detailed discussion between the patient and the specialist, during which the treatment options, expected benefits, and potential risks of each option are explained.
The Difference Between Vaginal, Abdominal, and Laparoscopic Hysterectomies
| Comparison Element | Vaginal Hysterectomy | Abdominal Hysterectomy | Laparoscopic Hysterectomy |
|---|---|---|---|
| Surgical Incision Site | There is no external incision; the procedure is performed through the vagina. | A surgical incision in the lower abdomen (transverse or longitudinal) | Several small incisions (0.5–1 cm) in the abdominal wall |
| Duration of the procedure | Usually relatively shorter | It may take longer in complex cases | Moderate; may vary depending on experience and circumstances |
| Recovery Period | Faster (usually 2–4 weeks) | Longer (4–6 weeks or more) | Moderate to short (approximately 3–4 weeks) |
| Postoperative Pain | Usually less | Higher due to an abdominal incision | Below the abdomen and slightly above the vagina |
| Possible Complications | Bleeding, infection, bladder/bowel injury, vaginal prolapse | Higher risk of wound infection, incisional hernia, and adhesions | Injury to internal organs or blood vessels; complications related to intestinal gas |
| Cosmetic Results | There is no external scar | A visible scar on the lower abdomen | Small, inconspicuous scars |
Preparation Before a Vaginal Hysterectomy
Preparation for surgery involves a series of medical and administrative procedures designed to ensure safety and minimize complications. It begins with a comprehensive clinical evaluation that includes a review of the patient’s medical history, medications (including herbal supplements), and drug allergies. The appropriate type of anesthesia (general or regional) is determined, and its benefits and risks are explained.
Before the procedure, the patient is asked to follow specific instructions, such as fasting for several hours and discontinuing certain medications if necessary—particularly blood thinners. Prophylactic antibiotics are administered no later than 60 minutes before the surgical incision to reduce the risk of infection, and measures to prevent blood clots, such as compression stockings or anticoagulant medications, are used as needed.
In the operating room, the patient is positioned on her back with her legs secured (lithotomy position), and a urinary catheter is inserted to empty the bladder. A pelvic examination is performed under anesthesia to assess the size and mobility of the uterus and to check for prolapse or adhesions; the vagina is then sterilized, and the surgical field is covered with sterile drapes.
Steps in a Vaginal Hysterectomy
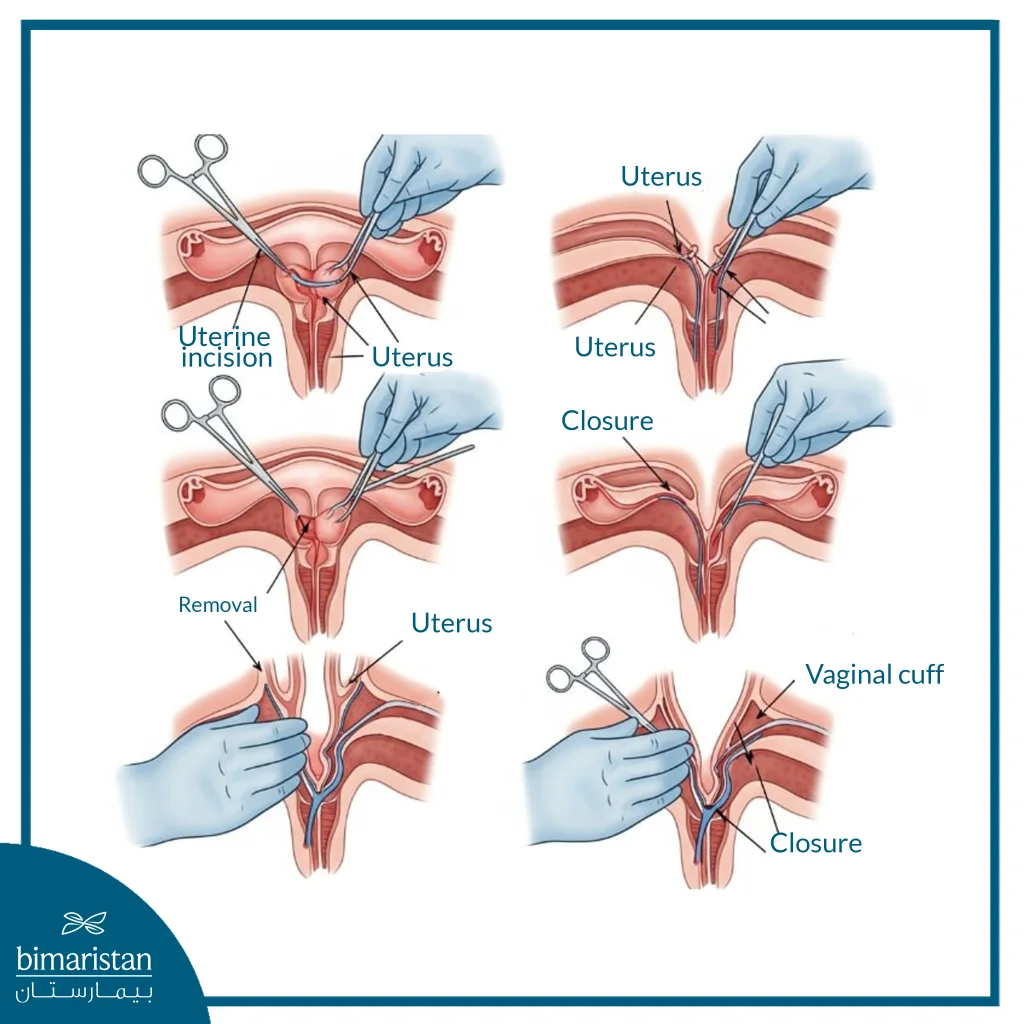
The procedure is performed vaginally without an abdominal incision and involves a series of precise steps:
- Making a circular incision around the cervix inside the vagina
- Separation of the bladder from the anterior portion of the uterus and opening of the anterior and posterior peritoneal spaces
- Identify and ligate the supporting ligaments (sacro-uterine ligaments and transverse cervical ligament), taking care to avoid the ureters
- Tie off and cut the uterine vessels securely to ensure control of bleeding
- Dissect the broad ligament, the round ligament, the utero-ovarian ligament, and the fallopian tube according to the surgical plan
- Completely free the uterus and remove it through the vagina
- Ensure that bleeding has stopped from all surgical sites
- The vaginal vault is closed with absorbable sutures; additional reinforcement may be performed to support the pelvic floor if necessary
If the uterus is enlarged, it can be divided into smaller sections to facilitate its removal, provided that the presence of malignancy has been ruled out.
Duration of a Vaginal Hysterectomy and Hospital Stay
The procedure typically takes between 60 and 120 minutes, depending on the size of the uterus, the complexity of the case, and any accompanying procedures (such as repair of vaginal wall prolapse). After surgery, the patient remains in the recovery room for one to two hours for observation. In most cases, patients can be discharged from the hospital the same day, while some may need to stay overnight for observation, especially if they have chronic conditions or have undergone additional procedures.
Recovery Period After Vaginal Hysterectomy
Recovery after a vaginal hysterectomy is faster and less painful than after abdominal surgery. Full recovery usually takes 3 to 4 weeks. During the first six weeks, the following is recommended:
- Avoid lifting heavy weights (more than 6–7 kg)
- Refrain from vaginal intercourse until your doctor gives you permission
- A light walk every day to improve blood circulation
- Use sanitary pads when experiencing light spotting, which may last from several days to several weeks
You should see a doctor immediately if you experience heavy bleeding, a fever, increasing pain, persistent vomiting, or foul-smelling discharge. Psychologically, some women may feel relieved that their previous symptoms have disappeared, while others may need emotional support to cope with the loss of their ability to have children.
Potential Risks and Complications of Vaginal Hysterectomy
Although a vaginal hysterectomy is considered a relatively safe procedure, any surgical procedure carries risks, including:
- Severe bleeding during or after surgery
- Pelvic or urinary tract infection
- Injury to the bladder, ureters, or intestines
- Blood clots in the legs or lungs
- Complications Related to Anesthesia
- Subsequent vaginal prolapse
In some cases, the surgeon may have to convert the procedure to laparoscopic or open abdominal surgery if severe adhesions or technical difficulties are encountered during the operation. Adherence to careful preoperative evaluation, proper surgical techniques, and postoperative follow-up reduces the likelihood of these complications.
Life After a Vaginal Hysterectomy
Recovery after a vaginal hysterectomy is faster and less painful than after abdominal surgery, and full recovery usually takes 3 to 4 weeks. It is recommended to avoid heavy lifting and vaginal intercourse for six weeks, while sticking to light physical activity such as walking. You should see your doctor if you experience heavy bleeding or increasing pain.
The menstrual cycle stops permanently, and pregnancy is no longer possible. If the ovaries are preserved, hormone production continues until natural menopause; however, if they are removed, menopausal symptoms may appear. Psychologically, most women feel better as their symptoms subside, while some may need emotional support to adjust to the changes.
The Cost of a Vaginal Hysterectomy
The cost of a vaginal hysterectomy varies depending on the country, the hospital’s level, the surgeon’s experience, the type of anesthesia, the length of the hospital stay, and the associated pre- and post-operative tests. Additional procedures, such as vaginal prolapse repair or oophorectomy, also affect the final price. The following is an approximate comparison of costs in several countries:
| The State | Approximate Cost of a Vaginal Hysterectomy |
|---|---|
| Turkey | $3,000–$5,000 |
| Germany | $9,000–$15,000 |
| The United States | $15,000–$25,000 |
| Canada | $12,000–$20,000 |
In conclusion, vaginal hysterectomy is an effective and safe surgical option in appropriate cases, particularly when uterine prolapse or benign conditions that do not respond to conservative treatment are present. This approach is characterized by the absence of an abdominal incision, less pain, and a faster recovery compared to traditional surgery. However, the decision remains an individual one and depends on a thorough medical evaluation that takes into account the patient’s health status, the reason for the surgery, and her future wishes. A clear discussion with a specialist and a thorough understanding of all alternatives and potential risks are essential steps toward making an informed treatment decision.
Sources: