
Hormonal therapy for prostate cancer is one of the main pillars in controlling this disease, which depends on male hormones, especially testosterone, for its growth. This type of treatment aims to lower the levels of androgens or inhibit their effect on cancer cells, slowing down the growth of the tumor and limiting its spread.
Hormone therapy is used in advanced stages of the disease, or in combination with surgery and radiation therapy to optimize treatment outcomes. With the development of modern medicines, the quality of life and survival time for patients can be significantly improved.
What is the scientific basis for hormonal therapy for prostate cancer?
Prostate cells grow under the influence of androgens, the most important of which are:
- Testosterone
- Dihydrotestosterone
The testes produce the majority of the body’s testosterone, approximately 90-95%, while the adrenal gland produces the remainder. Testosterone binds to androgen receptors inside cells and triggers a series of genetic changes that stimulate cell division and growth. Reducing the level of androgens in the blood or preventing their binding to the receptors is a key step in controlling the progression of the disease, especially in stages that are metastatic or not amenable to surgical or radiation therapy.
Goals of hormonal therapy for prostate cancer
Hormone therapy is used in multiple contexts of prostate cancer management, including:
- Initial treatment of common conditions
- Intermittent therapy to minimize side effects while maintaining disease control
- Palliative treatment to relieve symptoms caused by bone spurs or urinary tract obstruction
- Adjuvant therapy before or after surgery or radiation therapy to reduce tumor size or prevent relapse
Integration with other treatments
Hormone therapy is often combined with:
- Chemotherapy in the metastatic stages
- Radiation therapy in advanced stages
- Immunotherapy or targeted therapy in resistant cases
Studies have shown that combining more than one treatment modality significantly improves overall survival and quality of life compared to using hormone therapy alone.
Types of hormonal therapy for prostate cancer
Hormonal therapy for prostate cancer includes several types:
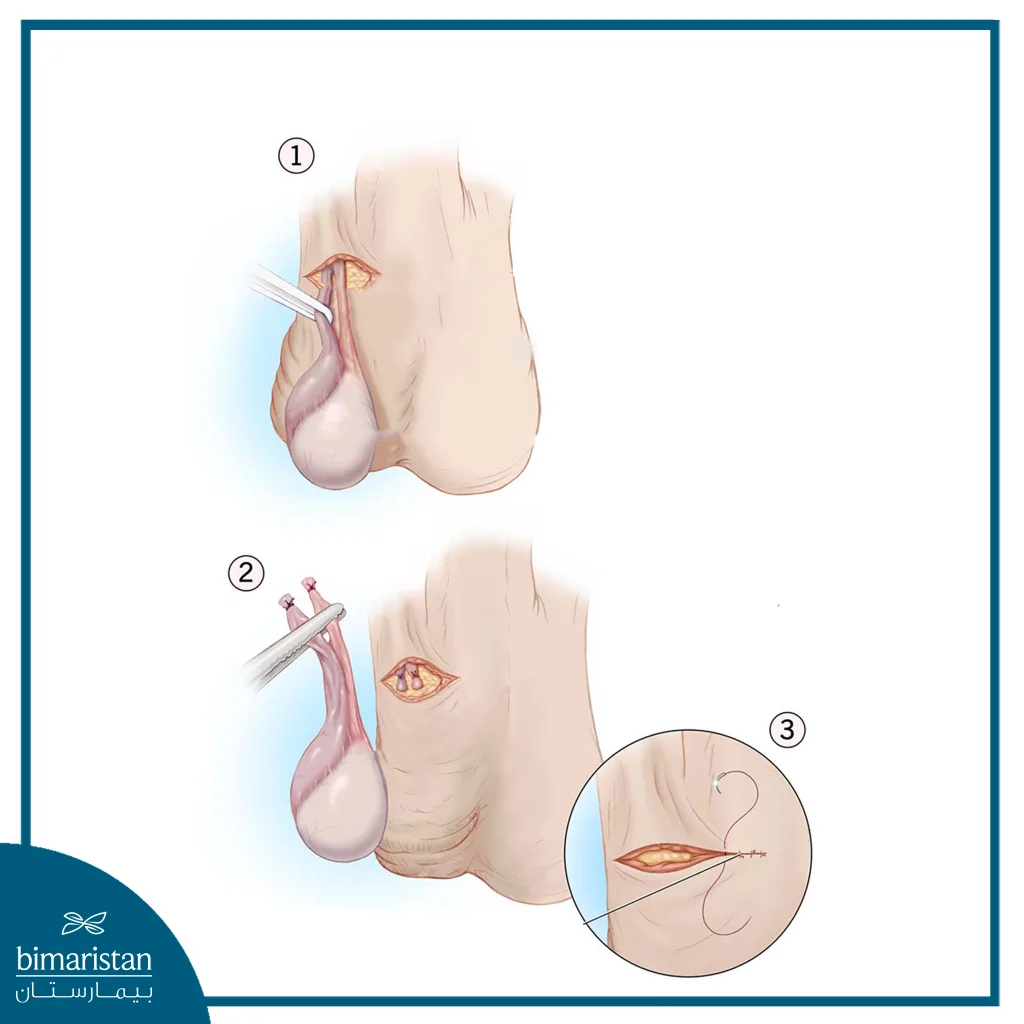
Surgical treatment (surgical castration)
This is the oldest form of hormone therapy and involves the removal of the testicles or androgen-secreting structures, resulting in a rapid and permanent drop in testosterone levels (below 50 ng/dL).
- pros:
- It does not require ongoing medication.
- Immediate and lasting effect on hormone levels
- cons
- Significant psychological impact resulting from testicular loss
- Side effects similar to long-term drug treatments, such as hot flashes, erectile dysfunction, and osteoporosis.
Gonadotropin-releasing hormone agonist drug therapy
This category includes drugs such as:
- Leuprolide
- Goserelin
- Triptorelin
These drugs stimulate the release of luteinizing hormone (LH) from the pituitary gland, causing a rise in testosterone levels in what is called the flare phenomenon. Then, with continued use, reverse inhibition of the LHRH receptors in the pituitary gland occurs, reducing the secretion of LH and FSH and leading to a sustained decrease in testosterone production from the testes. The primary disadvantage of this type of treatment is a temporary spike in testosterone during the first few weeks, which may exacerbate symptoms such as bone pain or urinary retention.
LHRH receptor antagonists
These drugs work by directly inhibiting LHRH receptors in the pituitary gland without initial stimulation, preventing the flare phenomenon and causing a rapid decrease in testosterone. Features include:
- Faster onset of action compared to triggers
- Safer for patients at risk of complications from temporary testosterone surges
Among them:
- Relugolix
- Degarelix
Antiandrogens
Used to inhibit the effect of androgens at the receptor level within prostate cells. Divided into:
- First generation: Block the binding of testosterone and DHT to the androgen receptor, but may show partial activity in some cases, limiting their effectiveness in advanced stages. Include
- Flutamide
- Bicalutamide
- Nilutamide
- Second generation (most advanced): Highly capable of blocking androgen receptor activation even in the case of mutations, especially used in castration-resistant cancer. Include
- Enzalutamide
- Apalutamide
- Darolutamide
Inhibitors of adrenal androgen production
Abiraterone acetate inhibits the CYP17A1 enzyme responsible for the synthesis of androgens in the adrenal gland and tumor tissue. It is given with corticosteroids to avoid mineralocorticoid hyperplasia caused by inhibition of the hormonal pathway.
Patterns of application of hormonal therapy for prostate cancer
Depending on the patient’s condition and the doctor’s opinion, hormone therapy is applied in several patterns:
- continuous treatment
- The drug is given continuously to maintain low testosterone levels.
- Intermittent therapy
- Treatment is paused for specific periods once disease control is achieved, then restarted when tumor markers (such as PSA) rise. This approach is used to minimize side effects and improve quality of life without significantly impacting long-term control.
Side effects of hormone therapy
Despite the effectiveness of hormonal therapy for prostate cancer, it is associated with a number of androgen deficiency effects, including:
- General effects
- Increased fat and changes in its distribution
- Mood disorders and depression
- Hot flashes and night sweats
- General fatigue and loss of muscle mass
- Effects on the skeletal system
- Osteoporosis and increased risk of fractures
- Weakened bone mass with long-term use
- Metabolic and cardiovascular effects
- Insulin resistance and high blood sugar
- High cholesterol and triglycerides
- Increased risk of cardiovascular disease
- Effects on sexual function
- Loss of sexual desire
- Erectile dysfunction and temporary or permanent infertility
Resistance to hormone therapy
Over time, a tumor may show resistance to treatment despite low testosterone; this is known as castration-resistant cancer, and the resistance arises as a result of:
- Mutations in the androgen receptor
- Activating alternative molecular pathways for growth and division
- The production of androgens within the cancer cells themselves
At this stage, newer generations of antiandrogens, androgen synthesis inhibitors, or chemotherapy are used in some cases.
Monitoring and follow-up of hormonal therapy for prostate cancer
The effectiveness of hormonal therapy for prostate cancer requires careful monitoring via:
- Radiography when spread or resistance is suspected
- Monitor bone density, lipid levels, and blood sugar levels
- Periodic PSA measurement (every 3-6 months)
- Assessment of serum testosterone to confirm that the castration threshold has been reached (< 50 ng/dL)
Hormonal therapy for prostate cancer has been shown to be very effective in controlling the progression of the disease, especially in cases that are metastatic or not amenable to surgical treatment. Although treatment does not achieve a complete cure in all cases, it does contribute to relieving symptoms and improving quality of life. Recent advances in anti-androgens and hormone synthesis inhibitors have given doctors more precise and effective treatment options. Regular follow-up and integrating hormone therapy with other approaches remain the key to achieving long-term treatment results.
Sources:
- Cancer Research UK. (2024). Hormone therapy for prostate cancer. Retrieved October 26, 2025
- American Cancer Society. (2024). Hormone therapy for prostate cancer. Retrieved October 26, 2025
- Attard, G., Murphy, L., Clarke, N. W., Cross, W., Jones, R. J., Parker, C. C., & de Bono, J. S. (2021). Abiraterone acetate and prednisolone with or without enzalutamide for high-risk non-metastatic prostate cancer: A meta-analysis of two randomized trials. The Lancet, 399(10323), 447-460.