
Optic neuritis is an inflammatory condition that affects the nerve responsible for transmitting visual signals from the eye to the brain, often resulting in pain when moving the eye and temporary loss of vision in one eye. The condition usually occurs in young adults, especially women between the ages of 20 and 40, and can sometimes be the first sign of multiple sclerosis. In most cases, the patient gradually regains vision within weeks, but cortisone treatment may accelerate the improvement of vision.
What is optic neuritis?
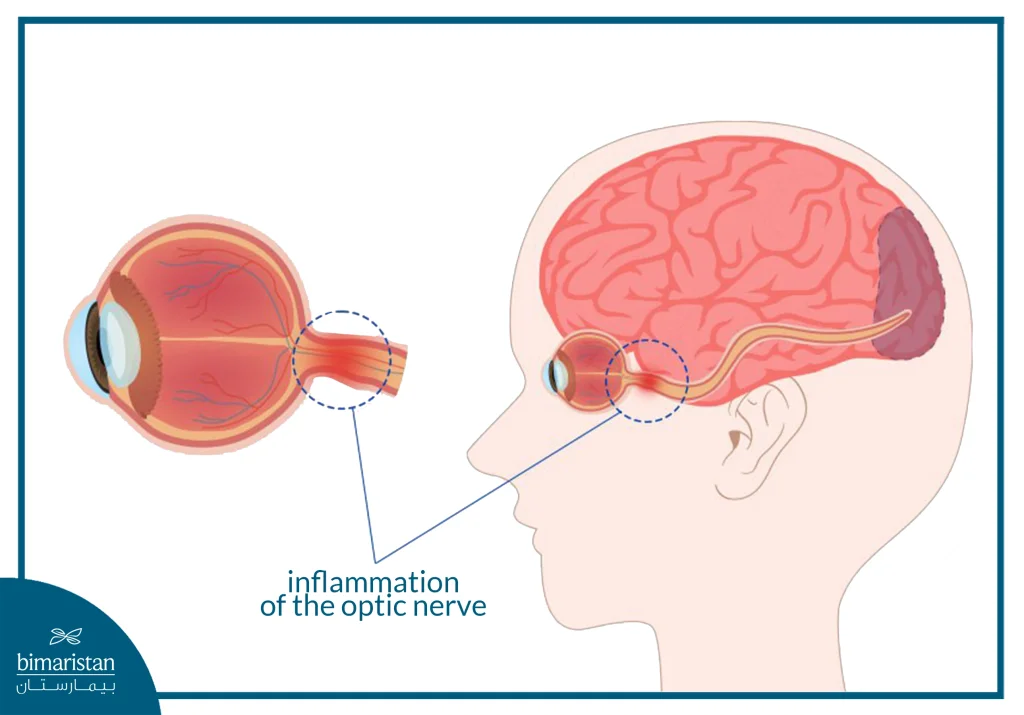
Optic neuritis: A type of neuropathy that occurs when nerve fibers become inflamed or swollen and damage the fatty sheath (myelin) that surrounds and protects the nerve. The optic nerve acts as a communication link between the eye and the brain, transmitting visual signals that allow humans to interpret images. When the myelin sheath is damaged, the transmission of nerve signals is disrupted and vision is impaired or distorted.
The inflammation may occur in isolation or as a result of immune-mediated diseases such as multiple sclerosis or lupus, and in rare cases due to optic nerve and optic medulla inflammation. It usually affects one eye, but in some cases it can affect both eyes. Symptoms usually start acutely and then gradually improve over 4 to 12 weeks.
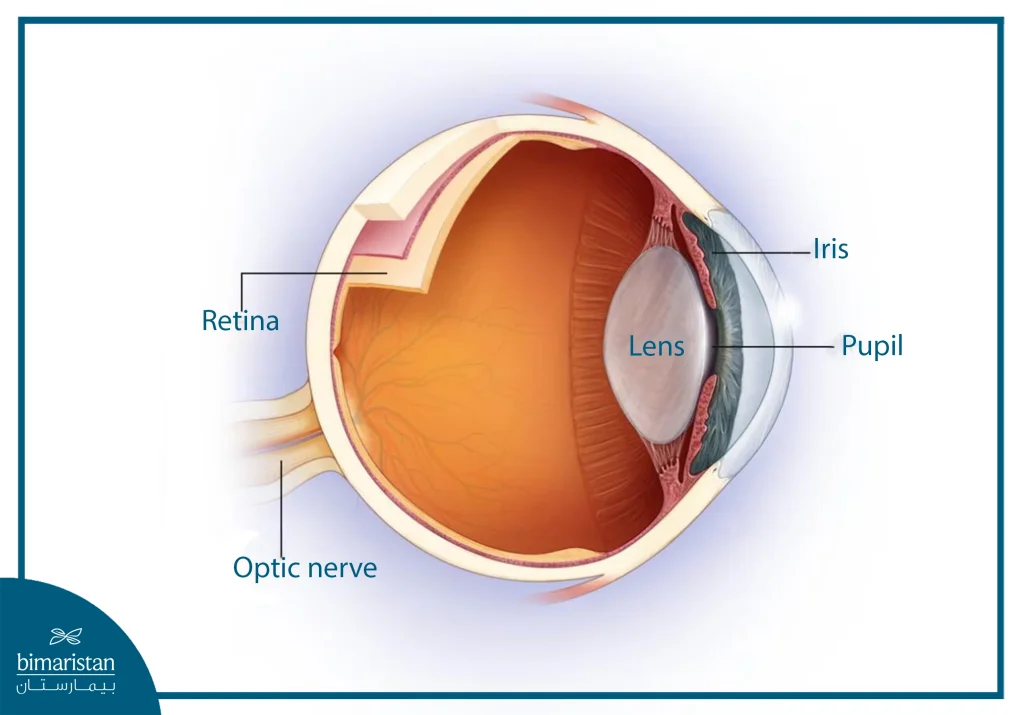
Types of optic neuritis
Types of optic neuritis fall into three main categories:
- Typical type: Usually affecting only one eye, vision loss is sudden and gradually regresses over days or weeks even without treatment, but treatment is recommended to accelerate improvement and reduce the likelihood of recurrence.
- Atypical type: Often affects both eyes, is characterized by more severe visual loss and slow improvement, and is usually associated with complex immunological and neurological disorders.
- Infantile type: It appears in childhood, and its symptoms are similar to the other types, but it has a better chance of recovery and faster recovery of vision compared to adults.
Causes of optic neuritis
Optic neuritis occurs when inflammation attacks the nerve fibers responsible for transmitting visual signals from the eye to the brain, damaging the fatty sheath (myelin) that protects the nerve. In many cases, the exact cause is unknown (called idiopathic inflammation), but there are multiple factors that can cause or contribute to inflammation, including:
Immune and inflammatory diseases
- Multiple sclerosis: The most common cause of the typical type of optic neuritis, about 50% of optic neuritis patients develop multiple sclerosis during their lifetime.
- Neuromyelitis Optica (NMO): Causes inflammation of the optic nerve and spinal cord, often more severe than MS.
- Oligodendrocyte glycoprotein antibody disorder (MOG Antibody Disease – MOGAD): Leads to recurrent inflammation of the optic nerve, brain, and spinal cord, with usually better improvement than NMO.
- Other immunologic diseases: SLE, Behcet’s disease, and sarcoidosis.
Septic infections
Infections can be a direct cause of optic neuritis, especially in children, and include:
- Viruses: There are several viruses that cause optic neuritis, the most important of which are
- varicella virus
- herpes simplex virus
- cytomegalovirus
- Human immunodiffencey virus
- Viruses transmitted by insects, such as fever mosquitoes
- Childhood viruses such as measles
- Bacteria: Bacteria vary in their effects on the optic nerve, but the most common are
- cat scratch fever
- Lyme disease
- tuberculosis
- syphilis
- fungi: Fungi are one of the most important causes of optic neuritis, and we mention the following
- Cryptococcus neoformans (cryptococcus disease)
- Types of Candida (candidiasis)
- Histoplasma capsulatum (Histoplasmosis)
- Aspergillus (Aspergillosis)
- Parasites, most importantly:
- Toxoplasma gondii (toxoplasmosis) is transmitted from cats
- Toxocara canis (canine toxoplasmosis) is transmitted from dogs
Drugs and poisons
Certain medications and toxic substances can damage the optic nerve, including:
- Medications to treat infections, such as ethambutol, chloramphenicol, isoniazid, and sulfa-type antibiotics
- Arrhythmia medications such as amiodarone and digoxin
- Malaria medications such as chloroquine and hydroxychloroquine
- Cancer medications such as methotrexate, vincristine, and tamoxifen
- Alcohol and methanol (wood alcohol) are used in paints and solvents
- Tobacco and nicotine
Other causes of optic neuritis
- Ischemia: When not enough blood reaches the optic nerve.
- Lack of vitamins: Especially vitamin B12, a deficiency of which leads to permanent nerve damage.
- Nerve compression: The result of tumors or increased intracranial pressure, such as hydrocephalus.
- Metabolic disorders: Like type 2 diabetes, the risk of nerve damage increases as blood sugar rises.
Symptoms of optic neuritis
Optic neuritis symptoms are centered around the eye and vision, often affecting only one eye, but can sometimes affect both eyes. Symptoms usually start suddenly or within a few days, vary in severity depending on the extent of the inflammation, and include the following:
- Eye pain: More than 90% of sufferers experience pain that increases when the eye is moved, and may take the form of a soreness behind the eyeball.
- Temporary vision loss or impairment: Vision deteriorates over hours or days, then gradually improves over weeks to months, and may be partial or complete.
- Blurred or cloudy vision: Blurred vision is especially common after an increase in body temperature, such as after a hot shower or exercise.
- Disturbance of the visual field: Partial loss of lateral or central vision, causing dark areas in part of the visual field.
- Poor color perception: Colors appear dull, especially red, and this is known as color dysphoria.
- Seeing flashes of light or flashing lights: The patient may notice flashes that appear when the eye is moved.
- Abnormal pupil response to bright light: The pupil may not constrict as expected when exposed to light.
Symptoms may worsen with fatigue or heat, but they often improve with time and proper treatment.
Diagnosis of optic neuritis
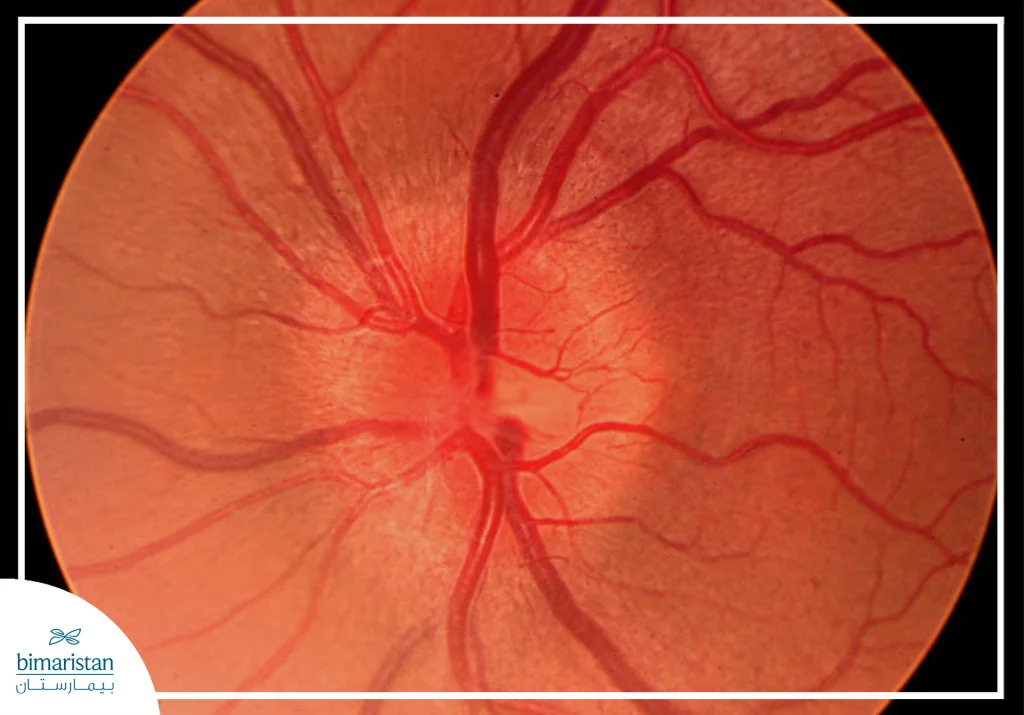
The diagnosis of optic neuritis is based on clinical symptoms, patient history, and a careful ophthalmic examination performed by an ophthalmologist or specialized neurologist. Diagnosis usually begins with a routine eye exam to assess visual acuity, color discrimination, and lateral field of vision, along with a pupillary response to light test, as the affected eye shows weaker narrowing when exposed to light compared to a healthy eye. The fundus is also examined using a slit lamp to directly view the optic nerve, as swelling of the optic disc is seen in about one-third of cases.
To confirm the diagnosis and determine the cause, a range of advanced tests are used, including:
- Magnetic resonance imaging (MRI): Shows areas of inflammation in the optic nerve and reveals brain lesions associated with MS or other immune disorders, such as NMO and MOGAD.
- Stimulated visual evoked potential test: Measures the speed at which visual signals travel from the eye to the brain, which is slower when there is damage to the myelin.
- Optical coherence tomography: Determines the thickness of the retinal fibers, which often decreases as a result of inflammation.
- Visual field tests: Show the extent of loss of side or central vision.
- Laboratory tests: These include blood tests to check for antibodies characteristic of autoimmune diseases such as NMO and MOGAD, or to detect the causative bacterial or viral infection, and sometimes a lumbar puncture may be required to analyze the cerebrospinal fluid.
The combination of these tests helps confirm the diagnosis and rule out other causes of vision loss, such as tumors or ischemia, allowing the right treatment to be started at the right time.
Optic neuritis treatment
Treatment for optic neuritis depends on the type and severity of the condition and the presence of comorbidities such as multiple sclerosis or immune disorders. The treatment plan aims to minimize inflammation, accelerate vision restoration, and prevent future relapse.
1. Cortisone therapy (primary treatment)
- Intravenous methylprednisolone at a dose of 500-1000 mg daily for 3-5 days is the standard treatment
- Intravenous therapy is usually followed by oral cortisone (Prednisone) in decreasing doses over 11 days
- Cortisone reduces inflammation and accelerates visual improvement, but it does not affect the final visual outcome in the long term
- Oral cortisone alone is not recommended without intravenous injection, as it increases the likelihood of inflammation recurrence
2. Advanced immunotherapies
Used in conditions associated with immune-mediated disorders such as neuromyelitis optica (NMOSD) or MOGAD, including:
- Rituximab
- Azathioprine
- Mycophenolate mofetil
These medications help lower the activity of the immune system and prevent relapse or new attacks.
3. Plasma Exchange (Plasma Exchange – PLEX)
- Used when there is no response to cortisone or in severe cases
- Removes antibodies and inflammatory substances from the blood
- Particularly useful in neuromyelitis optica (NMOSD)
4. Disease-Modifying Therapies (DMTs)
If there are brain lesions on the MRI that indicate a risk of multiple sclerosis (MS), it is recommended to use:
- Interferon beta
- Glatiramer acetate
- Natalizumab or ocrelizumab for advanced forms
These treatments help minimize relapses and delay the progression of MS
5. Auxiliary and supportive therapies
- Vitamin D: Keeping levels within the normal range helps support the immune system and reduces the risk of relapse.
- Medications with a neuroprotective effect: Citicoline and primonidine help protect nerve cells and support recovery.
- Visual rehabilitation: Using aids to improve vision and quality of daily life if partial visual impairment remains.
6. Surgical treatment (rare)
- It is used only in cases where there is mechanical compression of the optic nerve due to a tumor or mass
- Surgical drainage of the optic nerve sheath is performed to relieve pressure and preserve vision
7. Follow-up and visualization
- Periodic monitoring of visual acuity, color discrimination, and visual contrast
- Psychologically and visually support the patient if permanent vision issues remain
Complications of optic neuritis
In some cases, optic neuritis can lead to permanent or temporary complications, although most patients gradually regain their vision within a few months. Possible complications include
- Permanent damage to the optic nerve: Even after vision improves, most patients still have a small amount of nerve damage that has no obvious symptoms but may affect visual acuity in the future.
- Reduced visual acuity or poor color discrimination: The ability to see colors, especially red, may remain less clear than normal, and some patients may continue to have mildly impaired vision.
- Permanent visual loss: In a few cases, especially when the inflammation is recurrent or there are concomitant immune diseases, severe damage may lead to permanent visual loss.
- Side effects of cortisone therapy: These include increased susceptibility to infections, mood changes, weight gain, high blood sugar, and osteoporosis with long-term use.
Despite these complications, early treatment and careful follow-up significantly reduce the risk of permanent damage to the optic nerve and help preserve vision in the long term.
Preventing optic neuritis
There is no surefire way to prevent optic neuritis completely, as it can occur for immunologic or inflammatory reasons that are difficult to predict, but a healthy lifestyle and attention to controllable factors can minimize the risk of injury or relapse. The most important preventive measures include the following:
- Quit smoking all types of tobacco, including e-cigarettes and unburned tobacco products, as smoking negatively affects nerve and circulatory health
- Treat infections early before they spread or affect the optic nerve
- Adhere to your doctor’s instructions when using medications, and avoid taking any non-prescribed medication or drug substance.
- Maintain a balanced diet rich in B-group vitamins, especially vitamin B12, which is essential for nerve health.
- Moderate alcohol consumption and avoid toxins such as methanol found in some solvents or adulterated alcohol
- Managing chronic and immune-mediated diseases such as multiple sclerosis and lupus through regular medical follow-up and preventive treatment
Adhering to these measures helps minimize the chances of optic neuritis or recurrence and preserve long-term vision health.
Optic neuritis is a condition that is often reversible with early diagnosis and treatment, but neglect can lead to permanent nerve damage and vision loss. Bimarestan Medical Center in Turkey provides accurate diagnosis and advanced treatment under the supervision of specialized doctors to ensure the best chance of restoring and preserving vision.
Sources: