Trigeminal neuralgia is considered one of the most severe types of facial pain; it is sometimes described as “suicidal pain” due to its intensity. Studies indicate that the incidence rate is approximately 4–13 cases per 100,000 people annually, and it most often occurs in people over 50. The condition is characterized by sudden, severe episodes of pain resembling electric shocks, which may last for a few seconds or minutes. Early diagnosis and appropriate treatment contribute significantly to improving patients’ quality of life.
What is the trigeminal nerve?
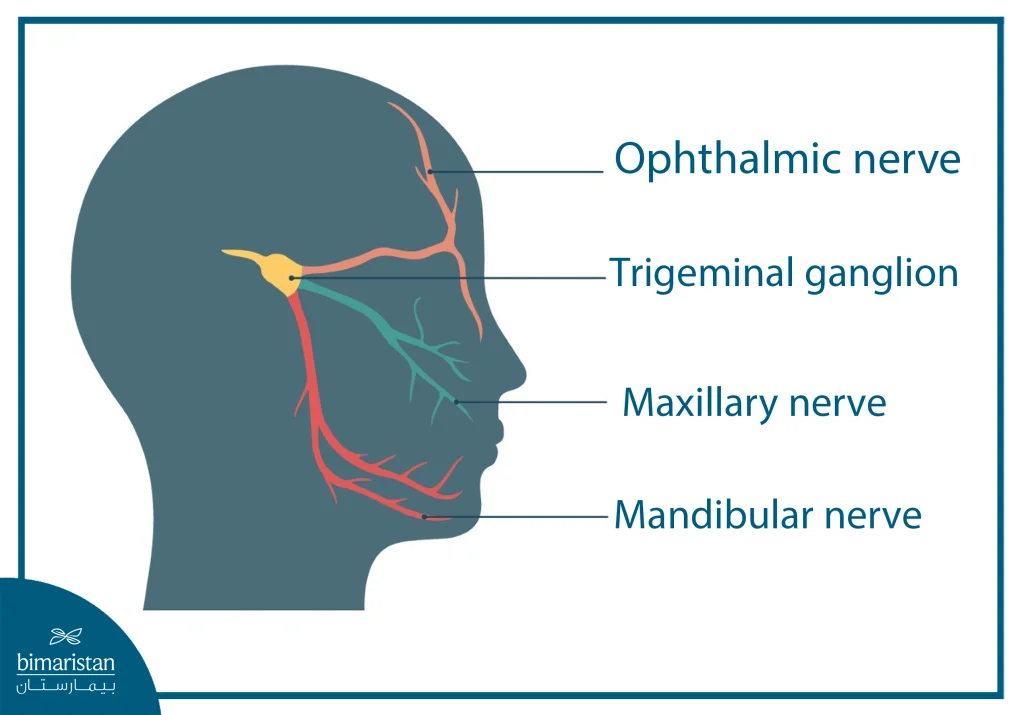
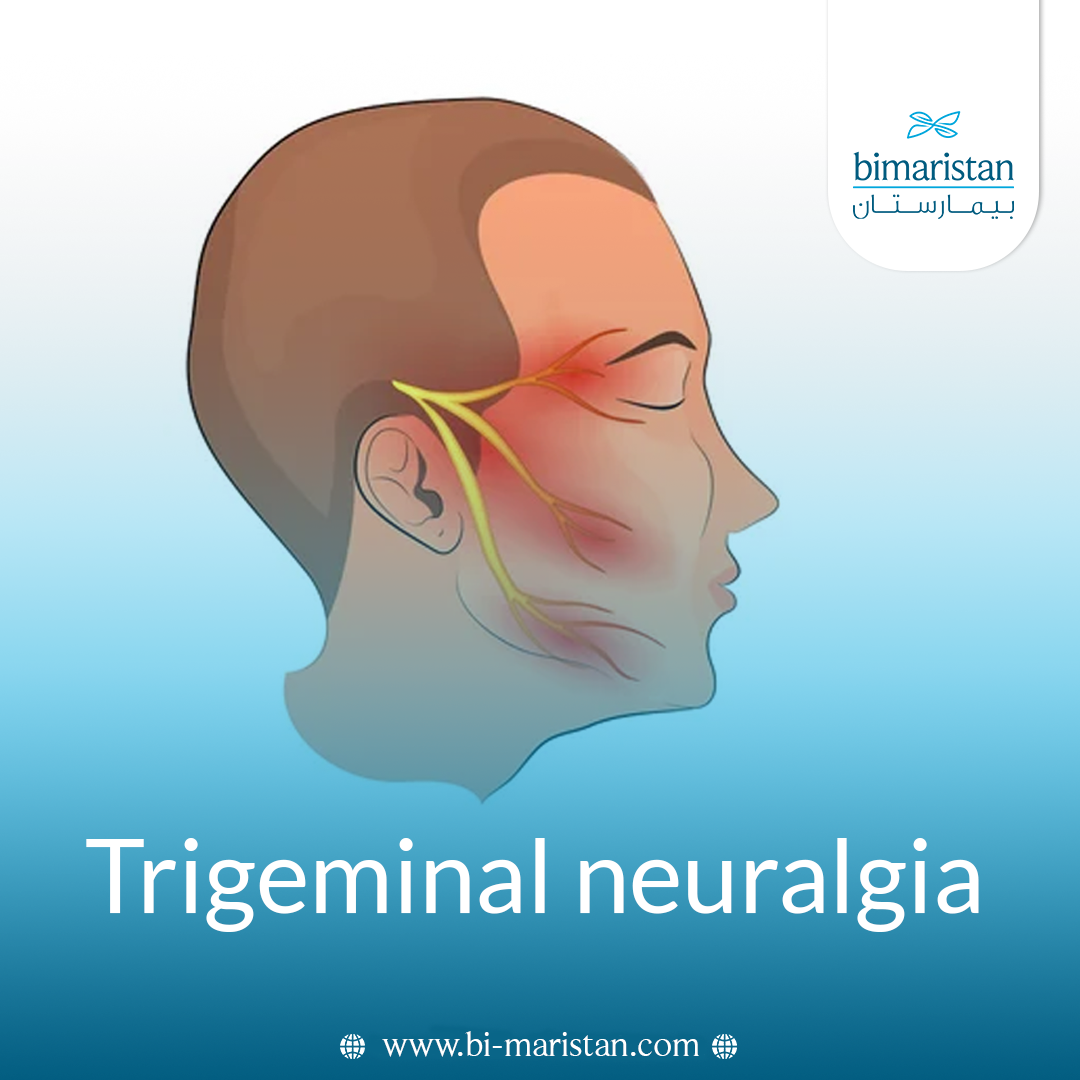
Trigeminal neuralgia is one of the most severe types of facial pain, caused by irritation or compression of the fifth cranial nerve (the trigeminal nerve), which originates in the brainstem within the skull. This nerve divides into three main branches:
- The ophthalmic branch (V1): transmits sensory input from the forehead, eye, and upper nose.
- The superior alveolar branch (V2): transmits sensation from the cheek, upper lip, and roof of the mouth.
- The inferior alveolar branch (V3): It transmits sensation from the lower jaw and lower lip, and controls the movement of the masticatory muscles.
When the trigeminal nerve is irritated or compressed, sharp episodes of pain, often described as electric shocks, occur on one side of the face. This disorder is also known as tic douloureux, or “painful facial tic,” due to the involuntary facial twitching triggered by the pain’s intensity. Pain attacks typically last from a few seconds to two minutes and may recur many times a day, with periods of remission between attacks. As the condition progresses, the attacks may become longer and more frequent, significantly impacting quality of life.
What causes trigeminal neuralgia?
The most common cause of trigeminal neuralgia is believed to be chronic compression of the nerve by a nearby artery or vein as it exits the brainstem, leading to irritation of the nerve fibers and episodes of pain. In some cases, the condition may be associated with damage to the nerve’s protective sheath (myelin), which disrupts the transmission of normal nerve signals and causes pain. This damage may occur in conjunction with multiple sclerosis or, less commonly, due to brain tumors.
In addition, certain other conditions can cause similar facial pain but are not true trigeminal neuralgia, such as tooth infections, sinusitis, shingles, postherpetic neuralgia, or previous facial injuries.
Who is at risk for trigeminal neuralgia?
Trigeminal neuralgia affects 5 out of every 100,000 people and is more common in women than in men; patients are typically middle-aged or older. Some people with multiple sclerosis also develop trigeminal neuralgia.
What are the symptoms of trigeminal neuralgia?
Patients describe trigeminal neuralgia pain as a sharp sensation resembling a prickling or a sudden stabbing; it may feel like a brief electric shock that usually lasts a few seconds, sometimes for a minute or two. An attack can be triggered by simple activities such as talking, chewing, drinking, or even a light touch to specific areas of the face called “trigger zones,” which are often near the nose, lips, eyes, or gums. As a result, some patients avoid eating, speaking, or even washing their faces for fear of triggering the pain. Other daily activities, such as shaving or brushing teeth, may also trigger attacks. The condition is typically characterized by the following features:
- In most cases, it affects one side of the face.
- It occurs as intermittent episodes that may last for weeks or months, interspersed with periods of remission lasting weeks or even years.
- Seizures tend to become more frequent and severe over time, which can significantly impact a patient’s life.
There is another type called atypical trigeminal neuralgia (Atypical TN), which is characterized by chronic, low-intensity pain
accompanied by a burning sensation or numbness, along with episodes of tingling similar to electric shocks. This type differs from the typical form in that it responds less well to conventional treatments and is sometimes difficult to manage.
How is trigeminal neuralgia diagnosed?
When a person first experiences facial pain, they often consult a primary care physician or dentist. If the pain requires further evaluation, a consultation with a neurologist or neurosurgeon may be recommended. The doctor will examine and palpate areas of your face to determine exactly where the pain is occurring and which branches of the trigeminal nerve may be affected.
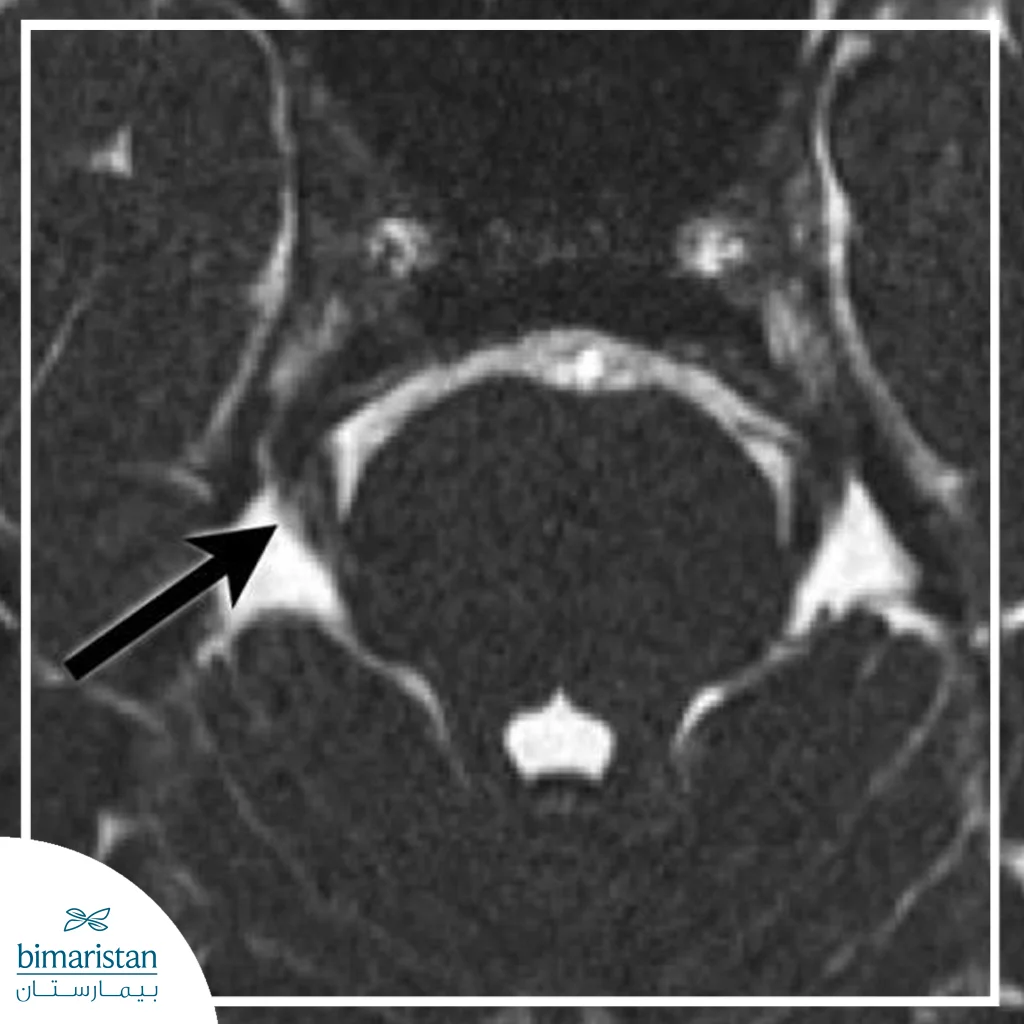
The underlying causes of trigeminal neuralgia are rarely serious; however, the possibility of a tumor or multiple sclerosis must be ruled out, which is why an MRI scan is usually performed. An MRI scan can detect any blood vessels compressing the trigeminal nerve, and trigeminal neuralgia is diagnosed following a careful evaluation of the patient’s symptoms.
Treatment for Trigeminal Neuralgia in Turkey
There are ways to treat trigeminal neuralgia, and a variety of treatments are available, including medication, surgery, needle procedures, and radiation. The first-line treatment is medication. When medication fails to control the pain or causes intolerable side effects, patients may consult a neurosurgeon to discuss other options.
Use of Medications
Over-the-counter medications such as aspirin and ibuprofen are not effective for trigeminal neuralgia; instead, anticonvulsants and muscle relaxants are prescribed to block pain signals from the nerve. These medications are the first-line treatment for trigeminal neuralgia and are used as long as the pain is controlled and side effects do not interfere with the patient’s activities. At least 80% of patients experience short-term pain relief with medication. For effective pain control, medications must be taken on a regular schedule to maintain a steady blood level.
The treatments listed above are used to manage trigeminal neuralgia, but if the medication begins to lose its effectiveness, your doctor may increase the dose or switch you to a different medication. Side effects may include the following:
- Nausea.
- Skin rash.
- Blood disorders.
- Drowsiness and loss of balance.
Therefore, patients are routinely monitored and undergo blood tests to ensure that the medication remains within safe therapeutic levels and that no blood disorders or complications develop. Combination therapy may be necessary to control pain (for example, using Tegretol with Neurontin).
Trigeminal Neuralgia Surgery
Trigeminal neuralgia surgery aims to relieve pressure on the nerve or stop the transmission of pain signals to the brain. These procedures are performed under general anesthesia and may require a one- or two-day hospital stay for observation.
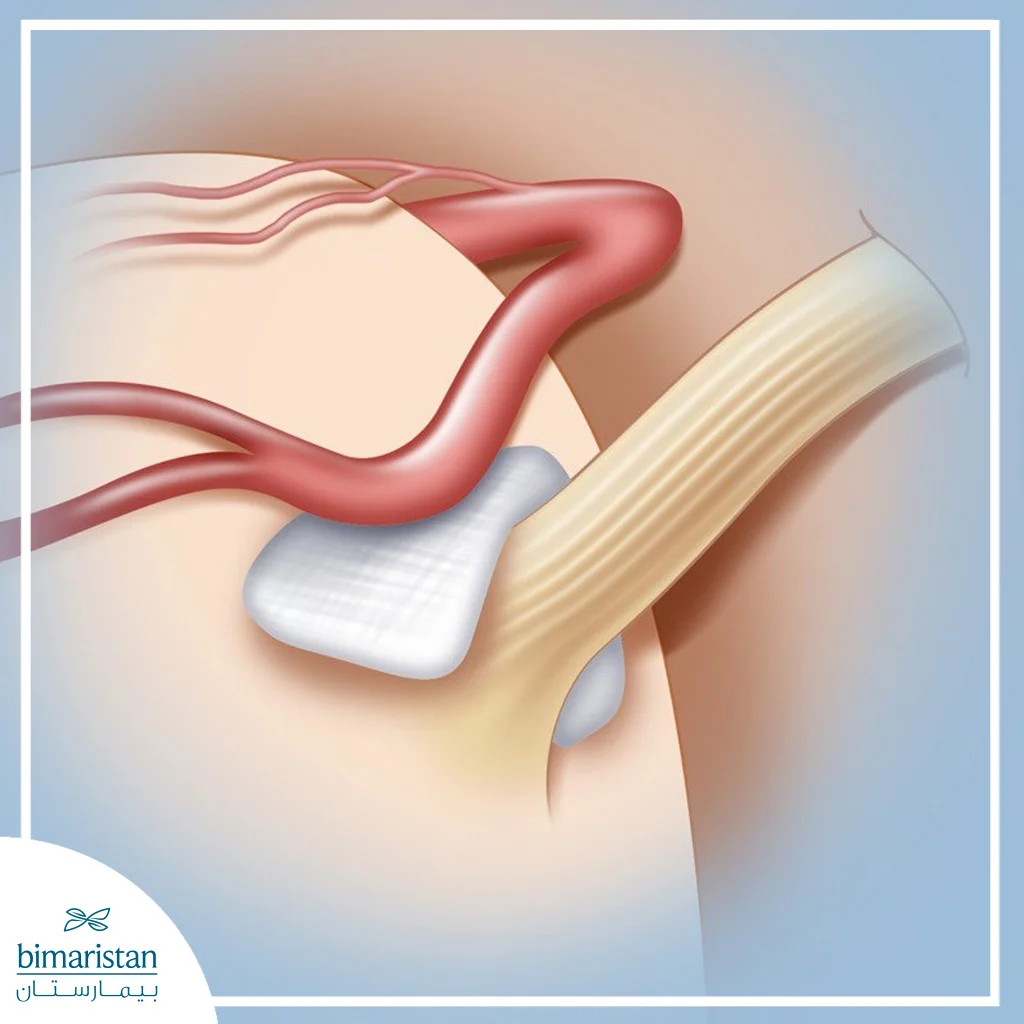
Microvascular decompression (MVD) is one of the most effective procedures. It involves repositioning the blood vessel, compressing the nerve, and placing a small Teflon patch to insulate and protect it. The procedure is performed through a small incision behind the ear in the skull. This surgery provides immediate pain relief for most patients, although symptoms may return over the years in some cases. It rarely causes facial numbness.
Dorsal selective rhizotomy involves cutting the sensory fibers of the nerve where it connects to the brainstem to prevent pain transmission, while preserving the fibers responsible for masticatory muscle movement. This procedure can result in permanent facial numbness, so it is often used for severe or recurrent cases that do not respond to other treatments.
A peripheral nerve can also be removed through a small incision in the face to sever a branch of the affected nerve, such as the supraorbital or infraorbital nerve, depending on the location of the pain. This procedure helps relieve localized pain but causes loss of sensation in the area supplied by the severed nerve.
Radiation Surgery for the Treatment of Trigeminal Neuralgia
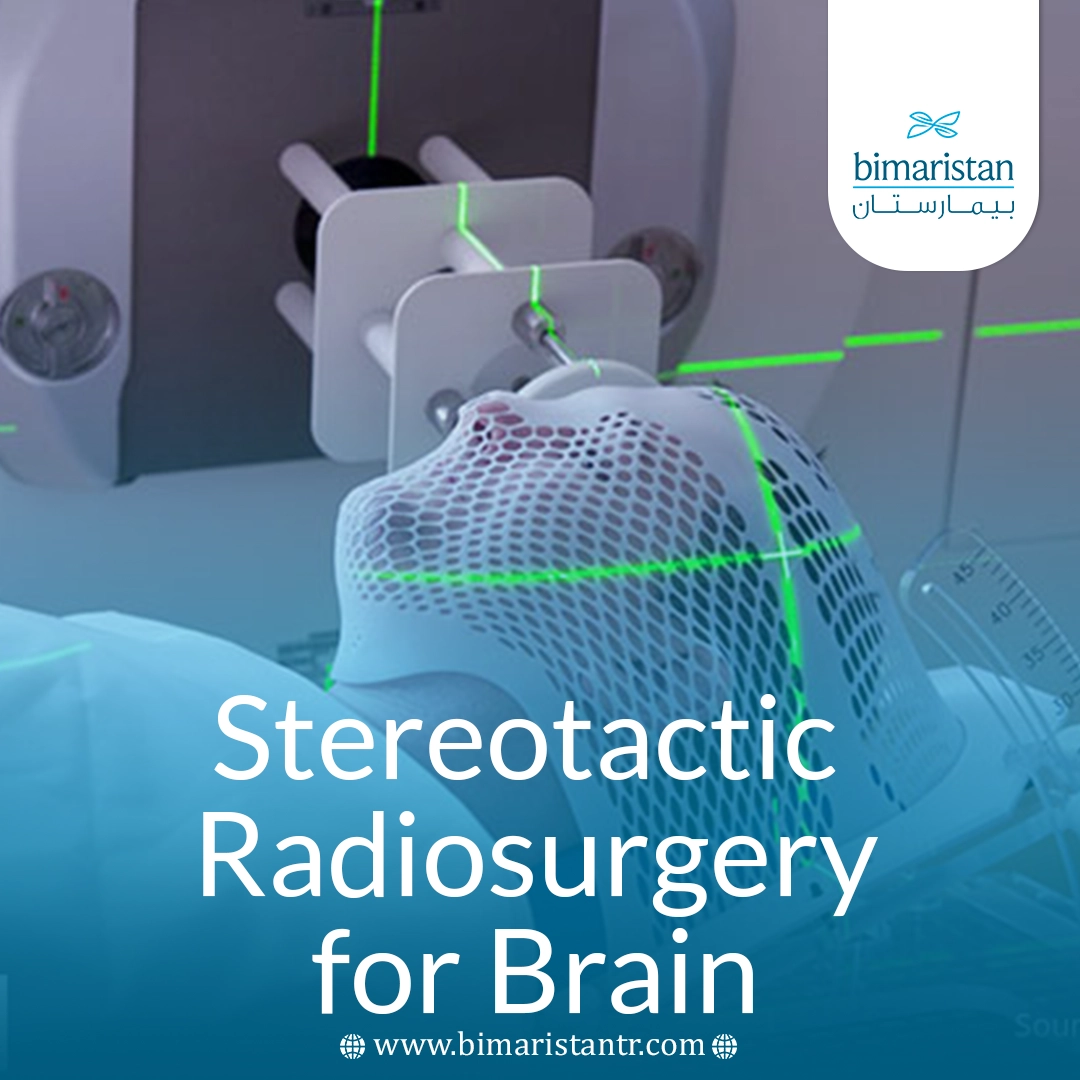
Stereotactic radiosurgery is a non-surgical outpatient procedure that uses highly focused radiation beams to destroy specific nerve root fibers causing trigeminal neuralgia. The two main techniques are the Leksell Gamma Knife and linear accelerator systems such as BrainLab Novalis. A head frame or stereotactic face mask is attached to the patient’s head to precisely locate the nerve on an MRI scan and to keep the head completely still during treatment. Highly focused beams of radiation are directed at the trigeminal nerve root, and in the weeks following treatment, a lesion (injury) may develop at the site of radiation.
Pain relief may not occur immediately but gradually over time; as a result, patients continue to take pain medication for some time, and the success of radiosurgery becomes evident when pain medication is reduced or discontinued. After 4 weeks, approximately 50% of patients will experience pain relief without medication or with reduced medication; after 8 weeks, 75% will. Complications include facial numbness and dry eyes, and in about 30% of patients, pain recurs 3 to 5 years after treatment. Repeat radiosurgery can be effective; however, the risk of facial numbness increases.
Outpatient Injection for Trigeminal Neuralgia
Needle procedures are minimally invasive techniques used to treat trigeminal neuralgia, in which the fifth cranial nerve is accessed through the skin using a hollow needle without the need for a large surgical incision or opening of the skull. The goal of these procedures is to selectively damage certain nerve fibers to prevent them from transmitting pain signals to the brain. This often results in varying degrees of facial numbness; this side effect is expected and necessary to achieve long-term pain relief. These procedures are typically performed under local anesthesia with a mild sedative in an outpatient setting, and most patients leave the clinic the same day.
Radiofrequency Root Extraction (PSR)
It is also known as transcutaneous stereotactic radiofrequency neurotomy. The procedure involves inserting a hollow needle with an electrode through the cheek into the nerve area. After the patient is anesthetized, they are temporarily awakened to pass a low electrical current that helps locate the source of pain through a tingling sensation; they are then re-anesthetized, and a precise thermal current is applied to destroy only the fibers causing the pain. This procedure provides immediate pain relief in over 90% of patients, but about 20% may experience a recurrence of pain within 10–15 years. Possible side effects include weakness in the jaw, loss of the corneal reflex, or facial numbness, which are usually temporary, while painful numbness is very rare.
Glycerol injection
The procedure involves inserting a hollow needle into the fluid-filled sac surrounding the trigeminal ganglion, then injecting glycerol to damage the fibers responsible for pain. However, precisely targeting glycerol is difficult, making the results less predictable than with other methods. This intervention provides immediate relief in about 70% of patients, but nearly half may experience a recurrence of pain within 3–4 years. Partial facial numbness is expected, and complications are typically similar to those seen with PSR.
Balloon pressure
In this technique, a catheter is inserted through the cheek into the trigeminal ganglion, and a small balloon is briefly inflated to compress the pain-causing fibers. After several minutes, the balloon is deflated and withdrawn. This procedure provides rapid relief in about 80–90% of patients, but about 20% may experience a recurrence of pain within 2–3 years. Side effects include facial numbness or temporary weakness in the chewing muscles, and rarely, double vision.
In conclusion, trigeminal neuralgia is a physically and psychologically debilitating condition; however, advances in modern medical techniques have made its treatment more effective and safer. From medication to microsurgery, there are multiple options available to manage symptoms and improve patient comfort, and seeking specialized care remains the most important step toward achieving the best outcomes. At the Bimaristan Medical Center in Turkey, patients have access to the latest treatment technologies administered by experts with extensive experience in this field.
Sources:
- National Institute of Neurological Disorders and Stroke. (2023). Trigeminal neuralgia fact sheet. National Institutes of Health.
- American Association of Neurological Surgeons. (2022). Trigeminal Neuralgia. AANS.
articles
-
Causes of Hypertension in Women and How to Treat It
-
A Guide to the Causes of Dizziness in Women

-
Stem Cells: Sources, Types & Benefits
-
Stem Cell Therapy For Diabetes in Turkey in 2025
-
The Most Advanced AIDS treatment

-
Cost of dental implants in Turkey: A Complete Guide for 2026
-
Cost of Hair Transplant in Turkey: A Complete Guide for 2026
-
Important Instructions After Surgery: What to Follow During Hospitalization

-
Essential Instructions to Follow Before Surgery for a Safe Procedure
-
Thirdhand Smoke

-
Limb Lengthening Cost in Turkey 2026: Affordable Surgery for a Taller You

-
Kidney Transplant Cost in Turkey: Breaking Down 2026 Prices, Safety, and Results

-
Laser Treatment for Vitiligo in Turkey: An Effective Solution

Cardiovascular
-
Port Catheter Placement: Central Venous Access Procedure in Turkey

-
Artificial Heart Transplantation
-
Minimally Invasive Heart Surgery in Turkey 2026
-
Open Heart Surgery
-
Cardiac Catheterization Procedure: A Final Solution to Heart Problems
-
Coronary Artery Disease: Causes, Symptoms, and Best Treatment Options
-
Congenital Heart Defects in Children: Causes, Symptoms, and Advanced Treatment Options
-
Aortic Surgery: Complete Guide from Diagnosis to Full Recovery
-
Cardiac Arrhythmias: Causes, Types, and Modern Diagnosis Methods
-
Heart Valve Treatment Without Surgery: Modern Non-Invasive Options
-
Carotid Artery Surgery: When Can It Prevent a Stroke?
-
Cardiac Resynchronization Therapy (CRT) for Heart Failure
-
Heart Failure Treatment: Symptoms, Causes, and Key Medical Options
-
Pulmonary Thromboendarterectomy (PTE): A Complete Guide to the Procedure and Outcomes
>> carotid
>> congenital heart
-
Transcatheter Ventricular Septal Defect Closure in Turkey in 2025
-
Tetralogy of Fallot in Children: Symptoms, Diagnosis, and Surgery Options

-
Symptoms of Heart Disease in Newborns: Early Signs & Detection Guide

-
Newborn Congenital Heart Defect Treatment: Complete Guide & Recovery

-
Pediatric Heart Surgery: Modern Techniques and High Success Rates for a Healthy Child

-
Norwood Procedure: A Surgical Hope for Children with Heart Defects

-
Atrial Septal Defect (ASD): Symptoms, Diagnosis, and Catheterization Treatment in Turkey
-
Patent ductus arteriosus (PDA) closure: Comprehensive understanding and modern treatment options
>> coronary artery
-
Coronary Stent Placement in Turkey: Procedure & Cost Guide

-
Off-Pump Coronary Bypass Surgery: Benefits, Procedure, Risks, and Success Rates

-
Coronary bypass surgery: A comprehensive guide to the procedure and outcomes

-
Minimally Invasive Direct Coronary Artery Bypass (MIDCAB) in Turkey

-
Causes of angina: Predisposing factors, symptoms and warnings
>> electrophysiologist
>> heart rhythm
-
Bradycardia: Causes, Symptoms, and Best Treatment Options

-
Pacemaker Implantation Surgery: Everything You Need to Know

-
Heart Palpitations at Rest Causes Explained: From Symptoms to Solutions

-
Atrial fibrillation catheter ablation: A comprehensive guide to treatment, procedures and outcomes
-
Wolff-Parkinson-White Syndrome: Causes, Signs, and Management
-
Atrial Flutter Ablation: Procedure, Benefits, Risks & Recovery
>> heart valve
>> >> heart-valve-replacement
-
TAVR (Transcatheter Aortic Valve Replacement) in Turkey.
-
Mitral Valve Replacement Surgery in Turkey: Procedure & Recovery

-
Minimally Invasive Aortic Valve Replacement: Procedure, Benefits, and Recovery

-
Surgical Aortic Valve Replacement: Procedure, Benefits, and Recovery Guide

-
Understanding Balloon Valvuloplasty: Safe Treatment for Heart Valve Disorders
- Robotic mitral valve replacement: The latest in cardiac surgery
-
Transcatheter Mitral Valve Replacement (TMVR): How Is It Performed, and When Is It an Appropriate Option?
-
Mitral Valve Repair Surgery: Procedure, Benefits, and Recovery

-
Aortic Valve Repair Surgery: Procedure, Benefits, and Recovery

-
Heart Valve Replacement Surgery: Types, Procedure, and Recovery Guide

-
Heart Valve Disease: Causes, Signs & Modern Treatments
-
MitraClip Procedure: A Minimally Invasive Solution for Mitral Valve Regurgitation
-
Aortic vs Mitral Valve Stenosis: Symptoms, diagnosis and treatment
-
Heart Valve Treatment Without Surgery: Modern Non-Invasive Options
-
Mitral Valve Annuloplasty: Understanding the Procedure and Its Benefits
>> interventional cardiologist

>> large aortic vessel


>> peripheral vascular
-
Endovascular Treatment Of Diabetic Foot in Turkey in 2026
-
Renal Artery Stenosis Symptoms and Treatment
-
Lymphangioma: Causes, Symptoms, and Best Treatment Options

-
Dialysis Fistula: What Is an Arteriovenous Shunt and How It Works

-
Peripheral Vascular Sclerotherapy in Turkey in 2025
-
Peripheral Vascular Angioplasty
-
Hemangioma Treatment
-
Varicose vein embolization: A modern solution to eliminate pain and improve appearance
-
Raynaud’s phenomenon: Causes, symptoms, treatment and prevention

-
Laser or Surgical Treatment for Varicose Veins: Which Option Works Best?
- Subclavian artery stenosis treatment: Symptoms, causes, catheterization and surgery options
dentistry
-
Surgical Guide to Dental Implants in Turkey 2025
-
Dentistry in Turkey
-
Gingivitis: Everything You Need to Know About Treating Inflamed Gums

-
Teeth whitening trays: Types, how to use, advantages and disadvantages

-
Types of Orthodontics and Treatment for Malocclusion
-
The Hollywood Smile: Secrets to Beauty and Attractive Teeth

>> endodontics
>> hollywood-smile
>> >> aesthetics
>> >> crowns
-
Dental Crowns
-
Dental Veneers: Difference Between Veneers and Lumineers
-
Teeth Whitening: Types and Precautions

-
Intraoral Scanner for 3D Digital Prints

-
Overjet Treatment with Clear Aligners
-
Laser Teeth Whitening: Advantages, Disadvantages, and Cost

-
EFZ Crowns: Combining Zirconium Strength & Emax Aesthetics
-
Zirconium Veneers in Turkey: Types, Benefits & Latest Tech

-
Removable Dentures: Types, Features, and Cost
-
The Latest Methods in CEREC dental crowns

-
Dental Restorations:Veneers and Crowns
-
Laser Dental Treatment: A Precise and Safe Choice
-
Fractured tooth treatment: Causes, Diagnosis, and Treatment Options
>> implant applications
-
All-on-Four Dental Implants
-
All on 6 Dental Implants and Their Installation
-
Same-day Implants in Turkey
-
Non-surgical dental implants
-
Swiss Straumann Implants : Precision and Excellence
-
American Dental Implants: World-Class Quality

-
Swiss Nobel Dental Implants: Precision and Quality in Dental Implantology
-
Bego German Dental Implants: Quality and Long-Lasting Results
-
German DXL Dental Implants: Quality in Dental Implantology

-
Medentika Dental Implants: Features and Cost
-
French Dental Implants: Features and Cost
-
Korean Dental Implants: Types, Features, and Prices
>> maxillofacial surgery
-
Salivary Gland Removal Surgery: What is it and How is it Done?
-
Tooth Extraction

-
Ludwig’s Angina Treatment

-
Overjet Treatment with Clear Aligners
-
Salivary Gland Cancer Symptoms and Treatment
-
Minimally Invasive Salivary Gland Surgery: Indications and Main Techniques
-
Severe Facial Fractures: Le Fort Classification and Treatment
-
The latest methods in Retrognathia treatment
-
Jaw Surgery Explained: Procedures, Risks, Costs, and Recovery
>> orthodontics
-
Surgical Orthodontics | Everything You Need to Know about It
-
Invisalign: Clear Removable Aligners
-
Bruxism Treatment | Causes of Day and Night Teeth Grinding
-
Deep Bite Treatment with Clear Aligners
-
Open Bite Treatment with Clear Aligners
-
Mouth Guard: For Athletes, Teeth Grinding and Snoring

-
Underbite Treatment with Clear Aligners

-
Overjet Treatment with Clear Aligners
-
Crowded Teeth Treatment with Clear Braces

- Ceramic braces: An effective cosmetic solution for accurate and discreet alignment correction
-
Lingual Orthodontics: Features, Drawbacks, and Cost

-
The latest methods in Retrognathia treatment
>> pedodontics
>> periodontology
-
Gum Surgery: Receding Gums Treatment
-
Tooth Sensitivity: Causes and Treatment Options
-
Gum Graft Surgery | Receding Gums Treatment for Cosmetic Reasons
-
Causes of bleeding gums: A simple sign or a warning sign of a serious illness

-
Dental scaling (teeth cleaning)

-
Gummy Smile: Causes, Treatment Methods, and Cost Guide

>> preventive-dentistry
-
Best toothpaste for cavities

-
How to Clean Teeth: Best Techniques for a Healthier Smile

-
Causes of tooth decay: How do they arise and how to prevent them?

-
Black tartar: Causes, damages, and removal methods in Turkey

-
Dental guard: Types, benefits, and how to choose the best guard to protect your teeth in Turkey
>> restorative

>> teeth health


eye diseases
-
Top 10 Causes of Blurry Vision (Foggy eyes)

-
Glaucoma Treatment

-
Eye Lens Disorders: Risks and Solutions
-
Retinal Diseases: Causes, Symptoms, and Treatment Options in Turkey
-
Oculoplastic Surgery: Restore Eye Beauty and Revitalize Your Appearance with Simple Steps
-
Corneal Disease: Common Types, Treatment Options, and Prevention Tips

-
Causes of double vision and modern treatment methods: A comprehensive guide for patients
-
Orbital decompression: Causes, symptoms and when is surgery necessary?
-
Recurrent Blurred Vision: When Is It a Serious Neurological Sign?

>> cornea
-
LASIK Surgery in Turkey 2026
-
Corneal Transplantation 2025

-
Astigmatism Treatment

- Farsightedness treatment in Turkey
-
keratoconus | symptoms and treatment methods

-
Nearsightedness and its treatment in Turkey

-
Treatment of keratoconus in Turkey
-
i-LASIK Surgery: Precision, Clarity, and Life-Changing Results
-
Conjunctivitis in Children: Causes, Symptoms, Treatment, and Prevention

-
Keratitis: Discover Its Causes, Symptoms, and How It’s Treated
>> lens

>> Lenses
-
Multifocal Lenses After Cataract Surgery: Benefits, Results, and What to Expect
-
Lens implants for severe hyperopia: The ultimate surgical solution
-
monofocal intraocular lens: Advantages, disadvantages, and when is it the best option?

-
Extended Depth of Field (EDOF) intraocular lens: Distortion-free, balanced vision

-
Toric lens: The precise solution for correcting astigmatism during cataract surgery

>> neuro
>> ocular oncology
>> oculoplastics

>> pediatrics

>> retina
-
Bionic Eye Implant
-
Hereditary Blindness Treatment with Stem Cell
-
Nyctalopia Causes and Treatment

-
Retinal Detachment Treatment in Turkey
-
Vitrectomy in Türkiye
-
Macular Degeneration: Causes, Symptoms, and Treatment Options to Preserve Vision

-
Diabetic Retinopathy Treatment in Turkey: Advanced Technologies for Vision Preservation
-
Central retinal vein occlusion: Causes, symptoms, and modern treatments
-
Macular Hole: Causes, Symptoms, and Surgical Repair for Vision Restoration
- Pneumatic retinopexy: A comprehensive guide to treating retinal detachment without surgery
-
Intraocular Injections to Treat Retinal Diseases: Efficacy and Treatment Method
-
Laser Treatment for Retinopathy: What You Need to Know
general
-
Breast Cancer

-
Organ Transplant in Turkey; The Future of Modern Organ Transplant

-
Types of Bariatric Surgery in Turkey

-
Abdominal Adhesions Causes and Treatment
-
Laser Hair Cyst Treatment
-
Esophageal Diseases: Comprehensive Guide to Common Disorders and Causes

>> abdominal-wall

>> bariatric
-
Laparoscopic Gastric Banding Surgery

-
Biliopancreatic diversion with duodenal switch in Turkey
-
Gastric Botox in Turkey | Best Treatment for Obesity 2026
-
Gastric Sleeve in Turkey 2025 | Best Results at Lower Costs
-
SADI-S (Single Anastomosis Duodeno-Ileal Switch)
-
Robotic Bariatric Surgery

-
Gastric Balloon in Turkey
-
Gastric Bypass Surgery (Roux- en-Y) in Turkey 2026
-
Latest Robotic Bariatric Surgeries
-
Mini Gastric Bypass: An effective solution for weight loss and obesity management
-
Learn about obesity risks for men and its impact on health

-
Gastric Plication Surgery: A Game-Changing Approach towards Obesity Treatment
- Revisional Bariatric Surgery: What It Is and Who Needs It
-
Bariatric Surgery and Fertility: How Weight Loss Surgery Affects Reproductive Health

-
Understanding the Difference Between Pancreatic Bypass and Gastric Sleeve Surgery
-
Causes of excessive Obesity and treatment methods

-
Your Guide to the Best Obesity Treatment and Long‑Term Weight‑Loss Success

- Laparoscopic gastric banding: Benefits and harms
-
Endoscopic Sleeve Gastroplasty (ESG): The modern technique for non-surgical weight loss
-
The SASI Surgery: A Comprehensive Guide to Understanding the Procedure, Indications, and Outcomes
>> breast-tumor
-
Mastectomy in Turkey
-
Breast Surgery: Procedures, Treatment & Recovery

-
Post-Mastectomy Pain Syndrome: When Is Pain After Breast Surgery a Concern?

-
Total Mastectomy: Between Fear and Hope
-
Breast Reconstruction After Mastectomy: The Journey of Hope

-
Breast Cancer Radiation Therapy: Why It’s a Key Step in Recurrence Prevention

>> colorectal
-
Colorectal Cancer Symptoms and Treatment Options
-
Chronic Anal Fissure Treatment
-
Laser Hemorrhoidoplasty | Latest Method of Treating Hemorrhoids
-
Hemorrhoids Treatment: Everything You Want to Know About It in Turkey
-
Rectal Prolapse Surgery
-
Colonoscopy in Turkey: Procedure, Benefits, and Preparation Guide
-
Anal Fissure: Main Causes and Treatment Methods
-
Hemorrhoid embolization treatment: Method, benefits and possible complications
-
Effective Anal Fistula Treatment: Best Options for Fast Recovery
-
Anal fistula causes and symptoms: Learn about the main causes and early symptoms

-
Laparoscopic Removal of Mucosal Colon Polyps in Turkey: Advanced, Minimally Invasive Treatment
-
Anal Stenosis Treatment: Causes, Modern Treatments & Prevention Tips
-
Pediatric Appendicitis Treatment: A Comprehensive Guide for Parents

-
Ulcerative colitis treatment in Turkey
-
Partial colectomy: When is it recommended and what are the results of the surgery?
-
IBS treatment methods: Symptoms and the latest treatments
-
Colostomy: Complete Guide to the Procedure and Post‑Op Care
-
The Difference Between IBS and Ulcerative Colitis: Symptoms, Diagnosis, and Treatment Explained
- Hemorrhoid banding: A Simple, Non‑Surgical Solution
-
Colostomy Complications: Causes, Risks, and Safer Alternatives
-
Stapled Hemorrhoidopexy: Benefits, Procedure Details, and Treatment Costs
-
Surgical hemorrhoidectomy: Risks and recovery period
-
Endoscopic anal fistula surgery: Minimally invasive technique
-
Colonscopic Ultrasound Procedure: Uses, Steps, and Recovery
-
Colon Cancer Resection: When It’s Needed and Available Surgical Options
-
Total Proctectomy: To treat rectal cancer
-
Transanal total mesorectal excision (TaTME): Advanced surgery to treat rectal cancer
-
Rectal cancer treatment: Latest methods by stage
- Anal fistula laser treatment: Healing without surgery
>> endocrine
>> >> thyroid surger
-
Splenectomy Procedure: Causes & Risks
-
Pediatric Splenomegaly Treatment

-
Thyroidectomy: Procedure, Risks, Recovery, and What You Need to Know
-
Laparoscopic adrenalectomy
-
Adrenalectomy: Procedure, Benefits & Hormonal Impact

-
Thyroglossal Duct Cyst: What It Is and How It’s Surgically Removed
-
Adrenal Cancer: Your Path to Recovery
>> esophagus
-
The latest methods of GERD treatment
-
Esophagus Disease Achalasia: All about it
-
Esophageal Atresia Treatment & Tracheoesophageal Fistula Repair Guide
-
Esophagus Disease Treatment: Latest Medical & Surgical Care
-
Esophageal Surgery: Indications, Procedure, and Success Rates
-
Difference Between Laparoscopic and Open Esophagectomy: Key Points

-
Preparation Before Esophageal Surgery: What You Need to Know
-
Post-Esophageal Surgery: Managing Pain, Nutrition, and Healing
-
Recovery After Esophageal Surgery: Timeline, Tips, and What to Expect

-
Esophageal Cysts: Diagnosis, Surgery, and Common Complications

-
Esophageal Surgery Complications: Key Risks to Know Before the Procedure
-
Esophageal Balloon Dilation: Everything You Need to Know
-
Esophagoplasty Surgery: When It’s Needed and What to Expect
-
Esophageal ESD: A Comprehensive Guide to Endoscopic Submucosal Dissection
-
Esophageal Perforation: Causes, Symptoms, Diagnosis, and Advanced Treatments in Turkey
-
GERD surgery: When to use it and what are the chances of success?
>> gastro
>> liver pancreas gallbladder tracts
-
Liver Hydatid Cyst Treatment
-
Gallstone treatment without surgery
-
Pancreatic Cancer: Latest Insights, Symptoms, and Treatment Options
-
Liver Cancer Treatment
-
Liver Fibrosis Symptoms, Causes and Treatment
-
Whipple Procedure for Tumors Treatment of the Head of the Pancreas and Duodenum
-
Hepatotoxicity Symptoms: The most important signs and treatment methods
-
Insulinoma Treatment: Modern Approaches and Managing Low Blood Sugar Symptoms
-
Liver Abscess Surgery: Indications and Best Treatment Options
-
Endoscopic removal of bile duct stones: The Complete Medical Guide

-
Robotic cholecystectomy (da Vinci): State-of-the-art surgical precision
-
Acute pancreatitis symptoms

-
Pancreatic Cancer Treatment: Surgery, Chemotherapy, and Modern Options
-
Treatment for Pancreatic Head Cancer: The Latest Surgical Methods and Cure Rates
-
Bile Duct Cancer: Symptoms, Diagnosis, and the Latest Treatment Methods

>> organ transplant
>> >> kidney-transplant
-
Kidney Transplant in Turkey
-
Robotic Kidney Transplant
-
After a Kidney Transplant
-
Pediatric Kidney Transplant: Causes, Procedure, and Outcomes
-
Liver Transplant Complications: A comprehensive post-operative guide
-
Liver Transplant Reasons and Post-Surgery Rehabilitatio
-
A comprehensive guide to liver transplant surgery: Causes, steps, conditions, and complications
-
Kidney Transplant in Turkey: A New Hope for Kidney Failure Patients
-
Liver Transplant for Children: Indications, Procedure, and Success Rates
-
Pancreas Transplant in Turkey: Procedures, Risks and Expected Results
-
Liver Transplant Surgery | Causes, Conditions and Risks
>> stomach-small-intestine
-
Duodenal Ulcer
-
Intussusception | Causes & Treatment

-
Stomach Cancer Symptoms and Treatment
-
Pyloric Stenosis Treatment: Effective Methods and Solution
-
Intestinal Fistula Surgery: Indications, Procedure Steps, and Recovery Explained
-
Endoscopic Treatment for Intestinal Obstruction: An Effective Alternative to Traditional Surgery
-
Small Bowel Stricture: Causes, Symptoms, and Treatment Options
-
Crohn’s Disease Surgery: When You Need It and Today’s Best Treatment Options
-
Ileostomy Explained: Procedure, Care, and Recovery Guide
-
Intestinal Volvulus: Causes, Symptoms, and Treatment Explained
General Ophthalmology
-
Best Eye Treatments 2026: Cutting-Edge Technologies for Lasting Vision Protection
-
Uveitis 101: Symptoms, Causes & Treatment Explained
-
Dry Eye Syndrome: Causes, Symptoms & Latest Treatment Options

-
Contact Lenses in Turkey: Types, Features, and Costs 2026

-
The latest technology in smart lenses

- ICL lenses in Turkey (intraocular lenses for vision correction): The advanced solution for vision correction without LASIK
-
Intraocular lens implantation in Turkey: Advantages and cost
-
Tear duct obstruction surgery: Causes and Surgical Treatment to Restore Normal Tear Flow
gynecology obstetrics
-
Infertility Treatment in Women – Latest Techniques with Injections and Stem Cells

-
Chronic cystitis in women

-
Common Gynecological Diseases in Elderly Women: Top Health Concerns and Treatment Options

-
Migraine Treatment During Pregnancy: What’s Safe?

-
Pregnancy Urinary Incontinence: Everything You Need to Know

-
Gynecologic Cancers: Types, Causes & Treatment Options

>> gynecologic oncology
-
Vaginal Cancer Causes, Symptoms and Treatment
-
Uterine Cancer: A Comprehensive Guide for Women with Endometrial Cancer in Turkey

-
Cervical Cancer | Everything You Need to Know About It
-
Oophorectomy: Indications and Alternatives

-
Gynecologic Cancer Treatment: Advanced Methods and Cure Rates

-
Radiation Therapy for Cervical Cancer: Types, Procedure, Effectiveness, and Side Effects
-
Bilateral salpingo-oophorectomy: Indications, steps and complications
-
Uterine Fibroid Ablation Treatment: When Is It the Best Option?
-
Vaginal Hysterectomy: A Comprehensive Guide to the Procedure, Benefits, and Risks
-
Laparoscopic Hysterectomy: Causes, Steps, and Postoperative Recovery
>> gynecology
-
Hysterectomy in Turkey in 2025
-
Laparoscopic Myomectomy
-
Vaginitis Treatment for Married women
-
Cervicitis: Causes & Treatment
-
Uterine Rupture: Causes & Treatment
-
Dilation and Curettage after Abortion

-
Uterine Fibroids Catheterization
-
Robotic Myomectomy in Turkey: Benefits, Procedure & Cost Guide

-
Laparoscopic Ovarian Cyst Removal in Turkey: Advanced Minimally Invasive Treatment for Optimal Healing

-
Vaginal Yeast Infection: Symptoms, Causes, Diagnosis, and Best Treatment Options
-
Premenstrual Syndrome: Hormonal Changes, Symptoms, and Relief Tips
-
Reasons for Hysterectomy: A Comprehensive Guide for Patients

- Laparoscopic oophorectomy
>> menopausal geriatric gynaecology
>> obstetrics



>> reproductive endocrinology infertility
-
IVF (in Vitro Fertilization)
-
Reasons for IVF Failure and Benefits of Plasma Injection into Uterus

-
IUI in Turkey: Intrauterine Insemination Procedure & Success Rates

-
The difference between IVF and ICSI
-
Infertility: Types, Causes, and Treatments

-
Irregular Periods: Causes, Warning Signs, and When to See a Doctor

-
Female Infertility: Causes, Diagnosis, and Effective Treatment Options

-
Endometriosis and Infertility: What’s the Connection?

-
Ovulation Weakness Treatment: A Complete Guide to Restoring Healthy Fertility
-
Ovarian Injection With Stem Cells: The Latest Infertility Breakthrough in Turkey 2026

-
Laparoscopic ovarian cystectomy: Causes, Procedure, Complications, and Cost
-
Laparoscopic Ovarian Drilling: An Effective Surgical Solution for Inducing Ovulation and Treating Polycystic Ovary Syndrome
-
Treatment of Polycystic Ovary Syndrome in Turkey: Medical Options and the Latest Technologies

>> urogynecology


internal-medicine
-
Kidney disease
-
Diabetes Disease: Causes, Symptoms & Effective Treatment Guide

-
Blood Disorders: The Hidden Danger and Ways to Stay Safe
>> diabetic disease

>> hematology
>> >> haemophilia
>> >> thalassemia
neurology
neurosurgery
- Scoliosis of The Spine | Symptoms & Treatment
-
Spinal Stenosis Causes, Symptoms, and Treatment
-
Alzheimer Disease Treatment and Prevention in Turkey

-
Parkinson’s Disease Treatment and Diagnosis in Turkey

-
Herniated Disc Operation
-
Types of Headaches

-
Cerebrovascular Diseases: Top Causes and Latest Treatment Options
-
Pituitary Tumors: Causes, Symptoms & Treatment Options

-
Skull Base Surgery: Types, Risks and Modern Treatment Options
-
Bell’s palsy surgery 2026: Latest Advances and Treatment Outcomes
-
Epilepsy Treatment in Turkey: A Comprehensive Guide to Seizure Management

-
Neuromuscular Disorders: A Journey to Understanding and Overcoming Challenges

-
Restless legs syndrome: Symptoms, causes, and treatments

-
Trigeminal Neuralgia: Causes and Modern Treatment Methods
-
Neck Pain with Hand Numbness: What It Means and When to Seek Help
>> alzheimer




>> cerebrovascular
-
Internal bleeding in the head

-
Brain Hemorrhage in Elderly
-
Endovascular Coiling for Brain Aneurysm Treatment

-
Cerebrovascular Disease Treatment: Breakthroughs in Modern Medical Care

-
Cerebral Hemorrhage Angiostomy Treatment: A Critical Emergency Intervention
-
Symptoms of sudden cerebral hemorrhage: How to recognize them and when to seek help?

-
Stroke Rehabilitation: Key Treatment Steps for Mobility and Speech Recovery

-
Stroke Prevention: Effective Ways to Lower Your Risk and Protect Your Health

-
Interventional Cerebral Artery Aneurysm Treatment: Techniques and Success Rates
-
Symptoms of sudden cerebral hemorrhage: How to recognize them and when to seek help?
-
After a cerebral hemorrhage: Major Complications and Recovery

-
Stroke in Elderly Adults: Causes, Symptoms, and Treatment Options

-
Transient Ischemic Attack: Causes, Symptoms, and Treatment Options

>> disc herniation
-
Epidural Steroid Injection
-
Laser Disc Decompression

-
Endoscopic Discectomy and its advantages in Turkey

-
Minimally Invasive Microdiscectomy
-
Cervical Disc Herniation: Symptoms and Treatment
-
Neck Pain
-
Cervical Spine Fusion surgery in Turkey: Techniques, Recovery Tips & Success Rates
-
Spinal Fusion Surgery: Benefits, Procedure, and When It’s Needed
-
Artificial Disc Replacement: A Modern Alternative to Spinal Fusion for Herniated Discs
-
Radiofrequency Disc Treatment: A Long-Term Solution for Pain Relief

-
Cervical Disc Causes Explained: Key Factors Behind Neck Pain

-
Disc herniation types: How do intervertebral injuries differ and which are the most serious?
-
Symptoms of vertebral compression on the nerves: When is it cause for concern?
-
Microscopic discectomy Surgery: Steps, Risks, Recovery Time, and Expected Results 2026

-
Ozone Therapy for Herniated Disc: A Modern Alternative to Surgery

-
Neck Disc Prevention: Essential Habits to Protect Your Spine
-
Neck disc symptoms: Early signs that shouldn’t be ignored

-
Dynamic Lumbar Stabilization : A Modern Solution for Relieving Back Pain While Preserving Mobility
>> epilepsy
>> headache



>> nerve surgery
-
Bell’s palsy surgery 2026: Latest Advances and Treatment Outcomes
-
Bell’s palsy laser treatment: A new technique to safely and effectively restore facial movement

-
Numbness and Tingling In Limbs: When It’s Neurological and How It’s Treated

-
Nerve Inflammation: Common Causes and How to Manage the Pain
-
Vagus Nerve Inflammation: Symptoms, Causes, and Treatment Options
>> neuro oncology
>> >> brain tumors
-
Awake Brain Surgery in Turkey
-
Exploring Brain Tumors Treatment: From Diagnosis to Recovery
-
Brain Tumor Surgery: Techniques, Risks, and What Patients Should Expect
-
Early Symptoms of Brain Tumors: Warning Signs You Should Never Ignore

-
Cerebellar Tumors Treatment: Advanced Approaches and Latest Medical Techniques

>> neurodevelopmental

>> neuromuscular

>> neurosurgery specialties
>> parkinson disease
-
Learn How the Prevention of Parkinson’s Disease Can Be Achieved

-
Causes and Symptoms of Parkinson’s Disease

-
Deep Brain Stimulation to Treat Parkinson’s Disease

-
The latest treatment for Parkinson’s disease: Focused Ultrasound for Parkinson’s Disease

-
Treatment of Parkinson’s with MRgFUS
-
Medical Fallacies About Parkinson’s Disease

-
DBS Battery Replacement: When Parkinson’s Patients Need It and Why

-
Parkinson’s Disease Stages: From Early Signs to Advanced Symptoms

-
Parkinson’s hand tremor: When is it an early symptom and how is it treated?

-
Transcranial Magnetic Stimulation for Parkinson’s : A Modern Technique to Improve Movement and Reduce Symptoms

-
Transcranial Pulse Stimulation for Parkinson’s Disease: An Advanced Technique to Improve Motor Symptoms and Quality of Life
-
Electrical Brain Stimulation for Parkinson’s Disease: An Advanced Technique to Improve Mobility and Quality of Life

>> pediatric neurosurgery
>> >> hydrocephalus

>> pituitary tumors
>> skull base tumors
>> spinal
>> spinal stenosis
>> spondylolisthesis


>> trigeminal neuralgia
oncology
-
Cancer Diagnosis and Treatment Methods
-
Interventional Radiology Cancer Treatments

-
Gallbladder Cancer Symptoms and Treatment
-
Tumor Embolization in Liver and Kidney Cancer: Methods, Advantages, and Risks
-
Multiple Myeloma: Symptoms, Diagnosis, and the Latest Treatment Methods
-
Bile Duct Cancer: Symptoms, Diagnosis, and the Latest Treatment Methods
-
Multiple Endocrine Neoplasia (MEN): Types, Symptoms, Diagnosis, and Treatment
>> interventional
>> medical oncology

>> radiation oncology

orthopedics traumatology
-
Bone Cancer Treatment
-
Hand Surgery: Techniques, Indications, and Patient Outcomes
-
Stem cells chronic fracture treatment
>> Bone fractures
-
Electrical Stimulation for Bone Healing in Turkey
-
Knee Fractures | Symptoms and Treatment in Turkey 2025
-
Osteoporosis Causes and Treatment
-
Femoral Fracture Surgery in the Elderly: Indications, Recovery Rates, and What to Expect
-
Osteoporosis After Menopause: Understanding the Silent Danger

-
Leg Fracture: From Diagnosis to Recovery Steps

-
Osteomyelitis: Symptoms, Causes, and Comprehensive Treatment

-
Femoral Neck Fracture: Causes, Symptoms & Treatment

-
Foot Fractures: Symptoms, Diagnosis, and Treatment
-
Fracture stabilization with bio-plates: Safe technique
-
Pelvic Fracture Treatment in Turkey
-
Step-by-step treatment of skull fracture in adults

-
Everything you need to know about the Ilizarov operation: Advanced Medical Solutions

-
Spinal fracture: Symptoms and Treatment
-
Shoulder fracture: Causes, Diagnosis, and Treatment

-
Finger Fractures: Clinical Assessment and Treatment Options

-
Wrist Fracture: Diagnosis and Treatment Methods

-
Metatarsal Fracture: from Diagnosis to Treatment

-
Ankle Fractures and Their Treatments

>> bone tumors
>> complex trauma

>> hand surgery orthopedics


>> joints
>> >> hip-replacement
>> >> knee replacement
-
Robotic Knee Replacement Surgery in Turkey 2026
-
Types of knee implants in turkey
-
Treatment of Osteoarthritis in Turkey
-
Partial Knee Replacement Surgery
-
Symptoms of Rheumatoid Arthritis and its Causes
- Rheumatoid Arthritis Treatment and its Diagnosis
-
Tibial Osteotomy for knee osteoarthritis: An Effective Alternative to Artificial Joint Surgery
-
Stem Cell Treatment for Knee Osteoarthritis: A Modern Solution to Regenerate Joints and Relieve Pain without Surgery
-
When Does Knee Osteoarthritis Require Surgery? Key Signs You Shouldn’t Ignore
-
Types of Knee Replacements in Turkey 2026
>> >> knee-arthroscopy
-
Hip Arthroscopy Procedure in Turkey 2026
-
Shoulder Replacement Surgery in Turkey
-
Elbow Replacement Surgery

-
Knee Arthroscopy Diagnosis and Treatment
-
Hip Replacement Surgery in Turkey
-
Stem Cells Injection for Knee
-
Knee Plasma Injection in Turkey 2025
-
Knee Gout Symptoms and Treatment
-
Causes of Swollen Knee and Treatment in Turkey
-
Symptoms of Arthritis in Women

-
Joint stiffness, Methods of Treatment in Turkey

-
Shoulder Dislocation Surgery
-
Knee Replacement Surgery
-
Shoulder Arthroscopy; Arthroscopic Joint Surgery
-
Treatment of Mild Knee Joint Effusion and its Diagnosis
-
Arthritis diagnosis, causes and treatments
-
Rotator Cuff Repair After Rupture: Restore Shoulder Function
-
Knee Osteoarthritis vs Meniscus Tear: Key Differences in Diagnosis and Treatment

-
Augmented Reality in Orthopedic Surgery: From Sci-Fi to Surgical Suite

-
Reverse Shoulder Arthroplasty Explained: Benefits, Procedure & Recovery
-
Hyaluronic knee injection price in Turkey
-
Elbow Joint Pain: Causes, Diagnosis, and Treatment Options

-
Hand joint dislocation; from diagnosis to treatment
-
Types of Artificial Shoulder Joints in Turkey
-
Stryker Joints: Types, Features, and What You Need to Know
>> lower limb
-
Hammertoe Treatment in Turkey

-
Limb Lengthening Surgery to Increase Height
-
Heel Spur: What is it, and How to Treat it
-
Leg Length Discrepancy; Symptoms and Treatment Method
-
Limb Lengthening With External Fixator: Realistic Results & Precise Steps

-
Height Lengthening Procedure with Internal Fixator: New Steps and Prospects
-
Everything you need to know about the Ilizarov operation: Advanced Medical Solutions
-
Types of Foot Arthritis and Their Treatment Options
- Everything You Need to Know About Swollen Ankles
-
Fitbone Intramedullary Nail for Limb Lengthening: Everything You Need to Know
-
PRECICE 2 Technique:Everything You Need to Know

-
The Best Osteonecrosis treatment
-
Knee osteoarthritis treatment in Turkey
-
LON Technique for bone lengthening: Method, Applications, Advantages, and Cost

-
Hammer Toe: Everything You Need to Know
>> pediatric surgery


>> spinal orthopedics traumatology
- Scoliosis of The Spine | Symptoms & Treatment
-
Lumbar Spondylolisthesis and Spinal Stabilization
-
Cervical Spondylolisthesis and Permanent Treatment for Neck Pain
-
Spinal Fusion Surgeries
-
Scoliosis Surgery: Journey From Diagnosis to Full Recovery
-
Endoscopic Spine Surgery for Herniated Disc: Effective Care
-
Arthroscopic Spine Surgery: A Minimally Invasive Breakthrough for Back Pain Relief
-
Minimally invasive spine surgery
-
Kyphosis treatment: A revolutionary solution for hunchback treatment

-
Ankylosing Spondylitis: Symptoms, Causes, and Effective Treatment Options
-
Lumbar stabilization surgery

-
Cervical bone spurs: Causes, symptoms and treatment
-
Everything About Bone Tuberculosis
>> sports injury
-
Shoulder Tendonitis: Causes & Treatment in Turkey
-
ACL Tear and Its Treatment
-
Knee Tendonitis Treatment in Turkey
-
Best Knee Braces Types in 2025

-
Heel Spur: What is it, and How to Treat it
-
Rotator Cuff Repair Surgery in Turkey 2025
-
Top Tennis Elbow Treatments, Causes, and Symptoms

-
Shoulder Tendonitis Treatment: A Step-by-Step Recovery Plan
-
Golfer’s Elbow: Symptoms and Treatment Methods in Turkey
-
Plantar Fasciitis: Causes and Definitive Treatment

otorhinolaryngology
-
Pharyngeal Surgery: Common Problems and Modern Treatment Options
-
Laryngeal surgery: When do you need it and what are the options?
>> facial plastic
>> head and neck


>> laryngology

>> otology
-
Auditory Brainstem Implant: Best Treatment Option for Deaf Patients
- Cochlear Implants Surgery
-
Bat Ears Treatment Without Surgery – Prominent Ear Cosmetic
-
Tympanoplasty – Procedure of Eardrum Patching
-
Eustachian Tube Dysfunction in the Ear and its Treatment
-
Mastoidectomy – Petromastoid Inflammation and Its Symptoms

-
Otoplasty: Simple Steps to Achieve a Natural Ear Shape
-
Stapedectomy: An Advanced Surgical Solution to Improve Hearing in Otosclerosis
-
Bone conduction implants: The modern solution for hearing restoration

-
Ossiculoplasty: Reconstruction of the middle ear bones to improve hearing
-
Cochlear implant in Turkey: Types and steps
>> paediatrics

>> rhinology
-
Functional Endoscopic Sinus Surgery: Sinusitis Treatment & Recovery Guide

-
Sinusitis

-
Septoplasty
-
Nasal Congestion Treatment

-
Adenoidectomy: All You Need to Know
-
Pediatric Rhinoplasty: When and Why Parents Should Consider This Procedure

-
Treatment of enlarged adenoids in children

-
Endoscopic Septoplasty: A Minimally Invasive Solution for Deviated Nasal Septum
-
Nasal Fracture Treatment: Manual and Surgical Response
>> sleep disorders

>> thyroid parathyroid
-
Thyroid Cancer: Signs, Symptoms, and Effective Treatment Options

-
Robotic Thyroidectomy
-
Thyroidectomy: Procedure, Risks, Recovery, and What You Need to Know
-
Hyperthyroidism Symptoms and Treatment

-
Parathyroid cancer treatment
-
Thyroglossal Duct Cyst: What It Is and How It’s Surgically Removed
-
Weight After Thyroidectomy: Causes & Effective Solutions
-
Life After Thyroidectomy: Key Facts You Need to Know
-
Parathyroidectomy: Indications, Types, and Risks
paediatrics surgery
>> general pediatric surgery
>> neonatal surgery
>> pediatric oncology surgery

>> pediatric thoracic surgery
Physical therapy for chronic pain
-
Ozone Therapy Explained: A Breakthrough in Modern Medical Science

-
Fibromyalgia Rehabilitation: Programs to Relieve Pain & Boost Life
-
Back pain treatment: The latest medical methods to relieve pain and restore mobility

-
Physical therapy for neck discs: The road to pain-free recovery without surgery

-
Neck Tendonitis: Symptoms and Methods of Treatment
physiotherapy
-
Robotic Rehabilitation Center in Turkey: Advanced Technology & Care

-
Child Rehabilitation Centers in Turkey: Comprehensive Pediatric Therapy Services

-
Neurorehabilitation
-
Latest Technologies for Prosthesis in Turkey

-
Physical therapy and Centers for rehab services in Turkey

-
Physical Therapy After Bariatric Surgery: Key to Recovery

-
Sports Physical Therapy: Boost Recovery and Enhance Athletic Performance

-
Geriatric Physiotherapy: Benefits, Techniques, and Role in Improving Quality of Life

-
Chronic Pain Physiotherapy: Modern Techniques to Improve Quality of Life
>> cardiopulmonary physiotherapy


>> children rehabilitation



>> geriatric physiotherapy

>> neurorehabilitation
-
Cerebral Palsy Rehabilitation: Essential Steps to Improve Mobility, Speech and Quality of Life

-
Rehabilitation for Patients with Multiple Sclerosis: Regaining Balance & Mobility

-
Parkinson’s Disease Rehabilitation: The Secret to Regaining Strength & Mobility

-
Brain Tumour Rehabilitation Guide: Proven Techniques for Faster Recovery
-
Rehabilitation After Brain Surgery: Key Steps and Why It Matters
-
Physical Therapy for Facial Paralysis and the Most Effective Rehabilitation Methods

>> orthopedic physiotherapy
-
Knee Osteoarthritis vs Meniscus Tear: Key Differences in Diagnosis and Treatment
-
Amputee Rehabilitation: Stages of Treatment from First Visit to Full Recovery

-
The Schroth Method for Treating Scoliosis: How It Works, Its Benefits, and Its Results

-
ACL Rehabilitation
-
Meniscus Surgery Rehabilitation
-
Hip Replacement Rehabilitation
-
Limb Lengthening Rehabilitation

>> prosthesis
-
Pediatric Prosthetics: The Key to Mobility, Independence & Care

-
Upper Limb Prosthetics: Restore Mobility and Quality of Life

-
Electronic Prosthetic Limbs: Revolutionizing Motion and Muscle Control

-
Water-Resistant Lower Limb Prosthetics: Unmatched Freedom in Every Environment

-
Sports Prosthetics: High-Performance Limbs for Amputee Athletes

-
Below-Knee Prosthesis: Types, Parts & How to Choose

-
Finger Prosthesis: Realistic, Precise & Confidence-Boosting
-
Silicone Limb Prosthesis: Benefits & Real-Life Uses
-
3D Printed Orthotics: Personalized Support for Optimal Comfort
-
Silicone Prosthetics: The Future of Aesthetic and Functional Restoration

- Types of Above-the-Knee Prosthetic Limbs: How to Choose, Benefits & Common Uses
-
Hand Prosthetics: Types, Features, and How to Choose the Right One

-
Above-Knee Prosthesis: Types, Benefits, and Mobility Restoration

>> sports physiotherapy

plastic reconstructive
-
Warts and its leading causes and treatment methods
-
Causes and treatment of callus
-
Ways to Remove Moles from the Face

-
Causes and Symptoms of Epidermoid Cyst

-
Burn Surgery: Steps Towards Healing and Full Recovery
-
Skin Cancers: Causes, Symptoms & Effective Treatment Guide
-
Pediatric Plastic Surgery Guide: What Parents Need to Know About Procedures and Outcomes

>> aesthetic
-
Bat Ears Treatment Without Surgery – Prominent Ear Cosmetic
-
Photodynamic Therapy

-
Gynecomastia Natural Treatment
-
Gynecomastia in Men, Causes and Treatment in Turkey 2025
-
Rhinoplasty: Complete Guide to Types, Benefits, and Costs
-
Body Sculpting and Liposuction in Turkey
-
Laser rhinoplasty: Fast and safe
-
The best age for rhinoplasty: When is the ideal time to have the procedure?

-
Laser liposuction in Turkey and its costs

>> burn surgery
>> dermatology
>> hair transplant
-
Benefits of PRP for Hair and Face in Turkey

-
Beard and Mustache Transplantation in Turkey

-
Hair Transplant in Turkey
-
NeoGraft Hair Transplant in Turkey

-
Robotic hair transplant in Turkey

-
Plasma Injection for Hair after Transplantation in Turkey
-
Hair Transplant for Women
-
Best FUE Hair Transplant & Its Cost

-
Benefits of Stem Cells Hair Therapy in Turkey
-
Treatment of Hereditary Baldness

-
Reasons for Hair Loss in Women and Its Treatment

-
Beard Hair Transplant Surgery in Turkey

-
Best Hair Transplant Technique in Turkey: DHI vs FUE Compared

-
FUT vs DHI Hair Transplant: Which is Better for You?

-
Hair transplants for children and teens: A comprehensive guide to causes and treatment

-
Nano Hair Transplant: Advanced Technology for Natural Results and Maximum Density
-
Hair Transplant Results: What to Expect

-
Exosome hair therapy: The latest in natural hair regeneration
-
Hair Care for Women: Proven Tips for Healthy, Shiny Hair

-
Causes of hair transplant failure: Top mistakes and factors that lead to unsuccessful results

-
Everything you need to know about hairline lowering surgery: Procedure steps and costs
-
Hair Transplant Longevity Explained: What Makes It More Permanent Than Natural Hair
-
Post-Hair Transplant Care Explained: Timeline, Do’s & Don’ts

-
Hair Transplant vs Medication: Which Hair Loss Treatment Works Best?
-
Sapphire Hair Transplant for Natural‑Looking, Lasting Results
- Eyebrow reconstruction: Modern techniques to treat eyebrow loss and restore a natural look in Turkey
-
Regenera Activa for Hair Loss: How It Works, Benefits, Side Effects, and Price

>> hand
>> microsurgery
>> pediatric plastic surgery

>> skin oncology
psychiatry
-
Understanding Depression Disorder: Causes and Prevention

-
Mental Health and Psychiatry Hospital

-
Schizophrenia Treatment in Turkey

-
Bipolar Disorder – Maniac Depressive Disease

-
Psychosis | Symptoms and Treatment in Turkey

-
The Best Treatment for Insomnia

-
Depression Symptoms in Men & Women of All Ages

-
The Best Severe Psychological Depression Treatment Methods

-
Depression Symptoms, Causes, and Treatment in Turkey

-
Stages of Addiction Treatment in Turkey: Complete Guide to Recovery

-
Addiction Treatment Center in Turkey 2026

-
Shabu Addiction (meth or crystal): Risks, symptoms, and treatment

-
Addiction Relapse: Causes and how to deal with it to avoid relapse

-
Bipolar disorder causes: Genetic, psychological and environmental factors

-
Bipolar disorder symptoms: Warning signs and stages of the illness

-
Autism Spectrum Disorder Treatment: Symptoms, Causes & Latest Therapies

-
Obsessive Compulsive Disorder: Discover Its Types and Associated Symptoms

-
Attention Deficit Hyperactivity Disorder (ADHD): Symptoms, Causes, and Effective Treatment Strategies

-
ADHD Treatment in Children: Symptoms, Strategies & Management Guide

-
Personality Disorders: Types, Diagnosis, and Effective Treatments Guide

-
Autism Spectrum Disorder: Understanding Differences & Supporting Children

>> addiction-treatment
-
Drug Addiction Treatment

-
Lyrica and Tramadol addiction: Symptoms, risks and treatment

-
Sexual Addiction: Understanding When Desire Becomes a Obsession

-
Heroin Addiction Treatment in Turkey: Step-by-Step Recovery Guide

-
Drugs Addiction: Symptoms, Causes & Prevention Tips

-
Opioids Addiction: From Pain Relief to Dependence

-
Cocaine Side Effects: Harms, Addiction Symptoms

-
Addiction Symptoms: How to Recognize & Overcome Substance Abuse Effectively

-
Ketamine: Uses, Effects, and Addiction Potential

-
Pornography Addiction: Causes, Symptoms, and Proven Treatment Strategies

-
Captagon Addiction Guide: Everything You Need to Know & Step-by-Step Treatment

-
Cannabis Addiction: Is It a Habit or a Disease That Needs Treatment?

- cocaine addiction treatment
-
Morphine Addiction: Causes, Symptoms & Effective Treatment Options

-
Shopping Addiction: Real Causes and How to Treat Compulsive Buying

-
Internet Addiction: The Invisible Chains Holding You Hostage

-
Behavioral Addiction: Types, Symptoms, and Modern Treatment Secrets

-
Gambling Addiction: The Illusion of Pleasure & Its High Price

-
Synthetic Cannabis Addiction: Symptoms, risks and treatment

-
Bonzai addiction: Causes, Symptoms, and Best Treatment Options

-
Video Game Addiction in the Digital Age—What You Need to Know

-
Caffeine Addiction: Breaking Free from the Silent Grip of Stimulants

- Alcohol Addiction: Start Recovery with Effective Support Programs
>> autism

>> depression


>> Eating Disorders



>> Personality disorders


>> schizophrenia

radiology
>> interventional neuroradiology
>> interventional radiology
-
Genicular Arterial Embolization
-
Cryotherapy for Cancer in Turkey: Alternative to Surgery?
-
Hyperthermia Therapy for Cancer
-
Radioembolization: Everything You Need to Know
-
Prostatic Artery Embolization: Blocking the Prostatic Artery
-
Inferior Vena Cava (IVC) Filter Placement: Indications, Procedure, and Potential Risks
>> radiation oncology radiology
thoracic
-
Everything You Need to Know About Video Thoracoscopy

-
Tracheal Diseases in Turkey: Symptoms Diagnosis & Treatments

-
Causes of Hyperhidrosis and Permanent Treatment in Turkey

-
Mediastinal Diseases: Causes, Types, Diagnosis and Treatment
-
Lung Cancer: Types, Symptoms, and Treatment Options
-
Thoracic Surgery in Turkey: A Comprehensive Guide to Modern Techniques and Surgical Treatment
-
Pulmonary Rehabilitation: How It Improves Breathing, Strength, and Daily Function
>> chest wall pleural diaphragm
-
Pleural Effusion: Types and Treatment Options

-
Hiatal Hernia Treatment
-
Exercises To Treat Pectus Excavatum in Turkey 2026

-
Broken Ribs Treatment in Turkey: Methods, Recovery & Care
-
Chest Wall Tumor Treatment: Types, Resection & Recovery Options
-
Diaphragm Pacing Surgery: A Breakthrough in Respiratory Technology
-
Laparoscopic Hiatal Hernia Repair: Benefits, Procedure, and Recovery Insights
-
Costochondritis and Its Treatment Methods

-
Pectus Carinatum (Pigeon’s chest) :treatment for chest protrusion
-
Mesothelioma: Causes, Symptoms, Diagnosis, and Treatment Options
-
Pneumothorax: Causes, Symptoms, and Treatment Options
>> hyperhidrosis


>> lung diseases
-
Pediatric Asthma Treatment & Management

-
Lung Abscess Treatment: Removal & Prevention Guide

-
Bronchial Asthma Treatment in Turkey | Causes and Prevention

-
Chronic obstructive pulmonary disease (COPD): How It Impacts Breathing and Treatment Options

-
Lung Volume Reduction Surgery: Boost Breathing & Enhance Quality of Life
-
Pulmonary Embolism Treatment: Causes, Symptoms, and Prevention Guide
-
COPD Treatment: Effective Steps for Easy Breathing

-
What is Tuberculosis? Causes, Types, and Mechanism of Infection
-
Tuberculosis treatment: The latest medications and protocols

-
Tuberculosis Diagnosis Explained: Early Detection and Treatment Options
-
Drug-resistant tuberculosis: Causes, Symptoms, and Modern Treatment
-
Tuberculosis prevention: The most important ways to protect yourself and those around you

-
Extrapulmonary tuberculosis: Types, symptoms, and different treatment methods

-
Tuberculosis in children: Symptoms, causes, and modern treatment methods

-
The role of surgery in tuberculosis treatment: When is it necessary and what types are there?

-
LVRS for Emphysema

-
Pulmonary Rehabilitation: How It Improves Breathing, Strength, and Daily Function
-
Thoracoscopic Lung Decortication: Indications, Procedure, and Recovery Time
>> lung-cancer
-
VATS Lobectomy
-
What’s New in Lung Cancer Treatment
-
Asbestos and lung cancer: How does exposure to asbestos increase your risk?

-
Squamous Cell Lung Cancer: The Deadliest Smoking‑Related Lung Cancer

-
Lung Adenocarcinoma: Causes, Symptoms & Treatment
-
Pulmonary nodules: Everything you need to know about early detection and follow-up
-
Lung cancer screening: The importance of life-saving CT scans
-
Small Cell Lung Cancer: Symptoms, Stages, and Treatment Options
-
Chemotherapy for Lung Cancer: Use, Side Effects, and Follow‑Up Care Explained

-
Immunotherapy for Lung Cancer: How It Works and When It’s Used

-
Proton Therapy for Lung Cancer: Uses, Benefits, and Key Advantages
- Large cell lung cancer: Causes, symptoms, diagnosis, and treatment options
-
Small Cell Lung Cancer Treatment Options: A Complete Guide
-
Lung Cancer: Types, Symptoms, and Treatment Options
-
Robotic Lobectomy for Lung Cancer: Achieving the Best Outcomes with Minimally Invasive Surgery
-
Lung Cancer Symptoms: Early Warning Signs You Should Never Ignore
-
Pancoast Tumor Overview: Causes, Symptoms, and Effective Treatment Strategies

-
Lung Cancer Surgery: Types, Success Rates, and Patient Outcomes
>> mediastinal
-
Pericardial Effusion in Turkey: Causes & Treatment Guide

-
Thymectomy Surgery: A Procedure to Treat Thymus Diseases
-
Superior Vena Cava Syndrome: Causes, Symptoms, and Treatment Options
-
Mediastinitis: Causes, Symptoms and Treatment
-
Mediastinal Mass Diagnosis: Key Methods to Identify the Nature of the Mass

-
Difference Between Anterior and Posterior Mediastinal Tumors: Causes, Symptoms, and Diagnosis
-
Follow-Up After Mediastinal Tumor Surgery: Complete Guide to Tests and Follow-Up Plans
-
Vats Mediastinal Tumor Surgery: Safe and Precise Chest Tumor Treatment
-
Mediastinal Cysts: Types, Causes, Symptoms, and Treatment Options

-
Mediastinal Diseases: Causes, Types, Diagnosis and Treatment
-
Immunotherapy for Mediastinal Tumors: A New Era in Modern Cancer Treatment

-
Robotic thymectomy: A Modern Technique for Precise, Minimally Invasive Surgery
>> trachea
-
Tracheal Stenosis: Causes, Diagnosis & Treatment Guide

-
Tracheal Surgery: Windpipe Procedures, Risks & Recovery Guide

-
Bronchoscopy in Turkey: Procedure, Indications & Recovery Guide

-
Esophagobronchial Fistula: Causes, Symptoms, and Treatment Explained

-
Bronchiectasis Treatment Guide: Latest Care and Therapy Options

urology
-
Kidney Stones Causes, symptoms & Treatment
- Treatment of Male Infertility
-
Urinary incontinence: Types, causes and treatment

-
Surgical Urethral Stricture Treatment: Causes, Symptoms & Options
-
Urinary Tract Infection: A Comprehensive Medical Guide
>> andrology
-
Latest Treatments for Varicocele
-
Hydrocele; Symptoms and its Treatment
-
Cryptorchidism Treatment: Undescended Testicle Surgery

-
Gynecomastia Natural Treatment
-
Success conditions of ICSI

-
ICSI Procedure

-
Varicocele Embolization: Advanced Non-Surgical Treatment Options in Turkey
-
Sperm Abnormalities Causes: Factors and treatments
-
Varicocele Causes: Prevention and Treatment
-
Penile Implants: The Ultimate Solution to Restore Confidence
-
Cystitis and Fertility: How Bladder Infections Affect Reproductive Health

-
Erectile dysfunction: Causes, Diagnosis and Treatment

-
Sexual and Fertility Problems After Spinal Cord Injury: Causes & Solutions

-
Laparoscopic varicocele surgery: To treat male infertility
-
Varicocele Embolization: Say Goodbye to Surgery
-
Weak Sperm: Causes, Symptoms, and Treatment Options

-
Microsurgical Varicocelectomy: The Most Advanced Approach to Varicocele Repair
-
Untreated Varicocele Effects: What Really Happens If You Ignore It

-
Varicocele Surgery for Treating Infertility
>> bladder urethra
-
Bladder Cancer Symptoms and Treatment
-
Urinary Tract Infection in Men | Causes, Treatment

-
Latest Neurogenic Bladder Treatment Methods in Turkey
-
Bladder Reconstruction (Neobladder) in Turkey
-
Transurethral removal of bladder tumour (TURBT)

-
Surgery for Vesicoureteral Reflux: An Effective Solution for Reflux Issues
-
Bladder Cancer Surgery: When It’s Needed and What the Risks Are
-
Cystitis in Women Explained: From Symptoms to Prevention
-
Surgical treatment of ureteral obstruction: Modern methods and success rate
-
Botox Neurogenic Bladder Treatment: Effective method
-
Artificial bladder implantation after cancer: A modern alternative to bowel use
-
Neurogenic Bladder Battery Explained: A New Era in Urinary Management
-
Urinary Tract Infection in Women: Causes, Symptoms, and Treatment

-
neuromodulation for neurogenic bladder treatment
>> kidney
-
Dialysis Fistula: What Is an Arteriovenous Shunt and How It Works
-
Early Kidney Failure Symptoms and its Treatment
-
Kidney Cancer Treatment; Turkey and Cancer Treatment at the Lowest Cost
-
After a Kidney Transplant
-
Pediatric Kidney Transplant: Causes, Procedure, and Outcomes
-
Robotic nephrectomy for kidney cancer: Accuracy, safety and speed of recovery

>> kidney stones

>> pediatric

>> prostate
>> >> chronic-prostatitis
>> >> prostate cancer
-
Robotic Prostatectomy
-
HIFU Treatment for Prostate Cancer in Turkey 2026
-
Radiation Therapy for Prostate Cancer: The Comprehensive Guide

-
Types of Brachytherapy for Prostate Cancer: The Complete Guide
-
Permanent Seed Brachytherapy for Prostate Cancer: A Precise and Effective Treatment Option

-
Understanding Prostate Cancer Stages and the Importance of Regular Follow-Up
-
Prostate specific antigen (PSA Test)

-
Hormonal therapy for prostate cancer: A comprehensive guide

-
Surviving prostate cancer: Physical and psychological challenges after treatment

-
Advanced Prostate Cancer Symptoms: Key Signs to Watch For

-
Prostate Biopsy: The Gold Standard for Prostate Cancer Detection
-
Prostate Robotic Radiotherapy in Turkey: Techniques, Benefits, and Outcomes

>> >> prostate hypertrophy
-
Benign Prostatic Hyperplasia Symptoms

-
Rezum Therapy for prostate without surgery 2026
-
Causes of Prostate Hypertrophy at an Early Age
-
Transurethral Resection of the Prostate in Turkey (TURP)
-
Prostatic Artery Embolization: Blocking the Prostatic Artery
-
HoLEP Laser Treatment for Prostate Enlargement in Turkey
-
“Transurethral Microwave Therapy (TUMT) for BPH: Benefits, Procedure, and Recovery
-
Laparoscopic Prostatectomy: Procedure, Benefits, and Recovery Explained
-
Treatment of Prostate Enlargement Without Surgery: Top Medical and Drug-Based Solutions